Select Page
A Golden Era of Cell-Assisted Brain Care Ahead

A Golden Era of Cell-Assisted Brain Care Ahead

A Golden Era of Cell-Assisted Brain Care Ahead

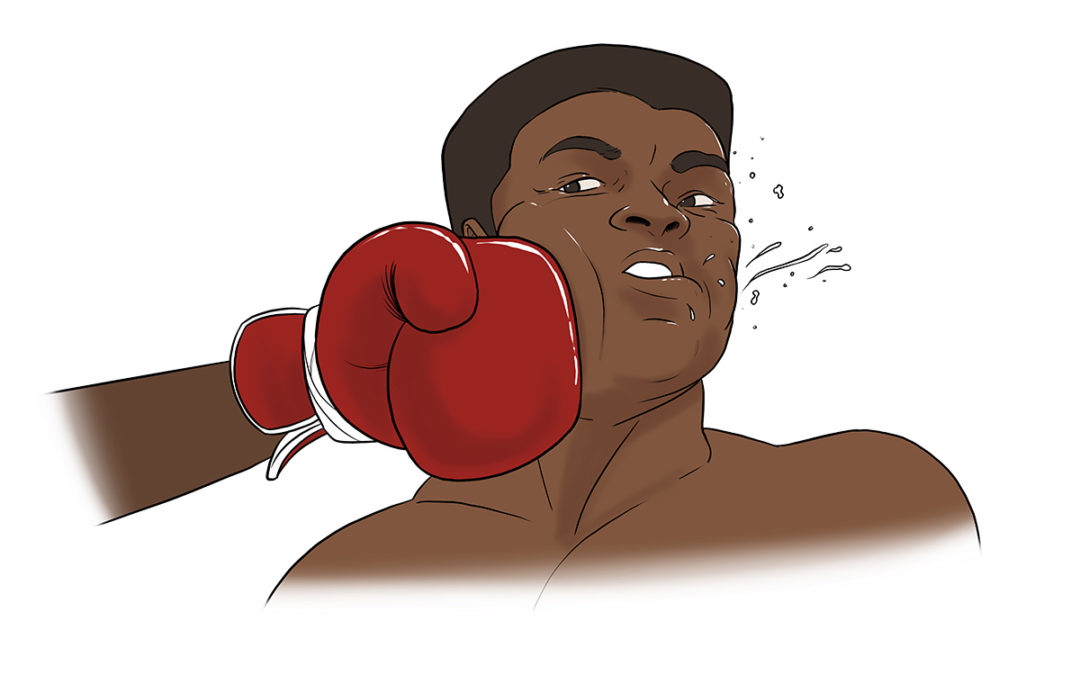
Muhammed Ali’s 1960 Olympic Gold medal started his ascent to being “The Greatest,” but the countless blows to his head – which he welcomed to tire his opponent out – ended in a years-long failed fight to save his brain.

In 2016, Parkinson-related issues took his life, though not before he sought out adult stem cell therapy. Unfortunately, Congress had not yet passed the Federal Right to Try Act of 2017.

What if those who first observed Ali’s slurring, shuffling, and memory struggles had known about the healing factors adipose-derived stem and regenerative cells (ADRCs) secrete?
And what if Ali had the Right to Try to access his ADRCs?

Would he have resumed floating like a butterfly and stinging like a bee? No, but that’s not the point, either.

Ali would have had a fighting chance at a better quality of life. Instead, he faced a decades-long struggle with his Parkinson’s symptoms and the PD drug’s side effects of nausea and tremors, not to mention the other medical conditions with which he lived.

Ali’s descent is a stark example of the risks of brain injuries to our long-term brain health.[1] And these risks are not unique to him or boxing.

Tim’s Win
“I raced in hundreds of powerboat races. Maybe I’m lucky…maybe I’m blessed…maybe I’m genetically superior…or maybe I’m all three, with help from my ADRCs!” says Tim.
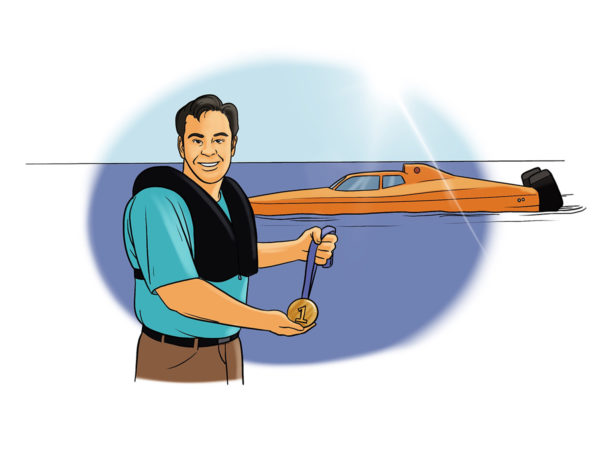
In 2000, Tim retired from offshore powerboat racing with four world speed records. He once hit upwards of 180 mph.

Arguably more at risk than Ali, he suffered innumerable head traumas, lost consciousness, and survived a near-death coma on the way to winning his Gold Medals.

In the early 2000s, Tim’s family and friends noticed his hands shaking. In 2008, a neurologist diagnosed him with essential tremors.

Essential tremor is a nervous system (neurological) disorder that causes involuntary and rhythmic shaking. It can affect almost any part of your body, but the trembling occurs most often in your hands — especially when you do simple tasks, such as drinking from a glass, handwriting, or tying shoelaces.

“The cause was a breakdown in the electrical connections in the nervous system due to adverse trauma,” Tim’s neuro explained. He forecasted continued deterioration.

Essential tremors are a suspected risk factor for Parkinson’s disease.[2] And as discussed in detail below, concussions significantly increase the risk of Alzheimer’s, Parkinson’s, ALS, and other neurodegenerative disorders.

Tim’s powerboat racing magnified the risk from contact sports. “It’s been determined that offshore race boat drivers experience more G forces in one race than all the astronauts in the history of NASA have experienced put together. The impact would come up your spine. My head would wobble like a bobble doll,” Tim explained.
“I must have had 1,000 concussions while racing. I probably went unconscious 100 times behind the wheel from the G-forces,” Tim estimated.

Before Tim had the “need for speed,” he played high school and college football. “This was in the days long-before helmet-on-helmet rules, and concussion protocols were in place. I remember getting hit in the head, going to the wrong sideline, and being put right back out on the field”, he recalled.

Tim also tells about his near-catastrophic motorcycle accident when he was a teen: “No helmet, of course…in the hospital for ten days…coma, severe concussion.”

Tim’s Right to Try
In March 2016, Tim accessed his ADRCs offshore with AMBROSE’s prior group. (Okyanos Cell Therapy, Freeport, Bahamas). Almost seven years later, he said, “I should be in much worse shape than I am.”

“My tremors are barely noticeable to other people now. I can eat soup without losing 2/3s of it between the bowl and my mouth. My writing isn’t perfect like I learned in Catholic school growing up, but I can sign checks and write legibly. My memory is fine.”

“The benefit of the stem cells is that it reconnected the wiring,” said Tim.

Tim credits his ADRCs-based cell therapy with other unexpected benefits:

  • “I wore glasses when I raced and before my treatment. Afterward, my vision improved to 20/20. I no longer wear glasses, including readers.” Tim is 63 years young.
  • After all the pounding on my ears and brain from racing and playing the drums in high school, I expected to be deaf by now.” he half-joked. “Instead, my hearing, senses of smell, and taste are better than they were before.”

Remarkably, Tim only recently developed high blood pressure and has no joint or spine issues.

Given Tim’s baseline and absence of other interventions, it would be difficult to attribute his sustained six-year improvement to anything other than his ADRC-based treatment.

Thus, we foresee a Golden Era of Brain Care ahead. More on that in a moment; first, some background.

Background
In the late 1970s, boxing fans observed changes in Muhammed Ali’s speed and speech. Others noted that Ali seemed bored and emotionally detached. The Greatest estimated his opponents hit him in the head 29,000 times – that is like being whacked in the skull day in and day out for 79 years.

And even in fights that he won, Ali took some vicious beatings, especially later in his career. He described the epic third fight with Joe Frazier, in which Ali retained his title after 14 brutal rounds, as “the next thing to death.”

In 1984, three years after retiring from the ring, Ali was diagnosed with Parkinson’s Disease (PD). At that time, doctors did not link the brutal poundings with PD.

Further, TBI research did not associate Ali’s brain damage with chronic traumatic encephalopathy (CTE), the term researchers use to describe a disease of the brain (encephalopathy) caused by repeated head traumas.

Nor did his doctors connect CTE to his frequent bouts of pneumonia, infections, or dementia.

Ali’s descent is a stark example of the risks of brain injuries to our long-term brain health.[3] And these risks are not unique to him or boxing.

CTE is Pervasive
Will Smith’s movie, Concussion brought public awareness to the devastation too many football players face later in life. NFL players are paid big bucks for taking three times the risk of dying from brain disorders than the fans watching them. That risk expands to four times for Alzheimer’s and ALS, respectively.[4]

In 2017, the Journal of the American Medical Association published a study revealing bleak futures for former NFL players. Their median age of death was just 67, and out of the 111 post-mortems, 99% — were diagnosed with CTE.

CTE symptoms vary depending on how advanced or severe it is, but people may experience memory problems, mood disorders, depression, and lapses in judgment.

Brain Trauma – Adding Insult to Injury and Injury to Insult

Brain trauma can be mild or minor, severe, or significant. You don’t have to be an NFL player, a boxer, or race powerboats to increase the probability of Alzheimer’s, Parkinson’s, and other neurologic problems.

After head trauma, some victims recover right away, but many suffer from a constellation of disturbances, including fatigue, poor memory, insomnia, pain, vision, speech, and balance difficulties. [5] [6]

Going the Distance from Brain Science to Brain Care
Ali had another fight separate and apart from his Parkinson’s battle: The chasm between the known factors contributing to neurological conditions and the treatment options available to patients suffering from them.

The gap became apparent in 2006 when Dr. William Langford, the first Chief Science Officer of the Michael J. Fox Foundation, published Parkinson’s Complex: Parkinsonism Is Just the Tip of the Iceberg.[7]

In short, Dr. Langford’s seminal paper stated PD was not limited to the loss of dopamine-producing neurons in the substantia nigra. Instead, Parkinsonism involves multisystem breakdowns. Therefore, he said, “Rather, we must deal with all aspects of the disease if we are to modify its progress in a way that truly enhances the lives of our patients over the long term.“

Subsequently, researchers discovered the same interconnected dysregulations after a TBI, stroke, spinal cord injury, Alzheimer’s, etc. Brain diseases don’t pull any punches – they spare no physiologic system.
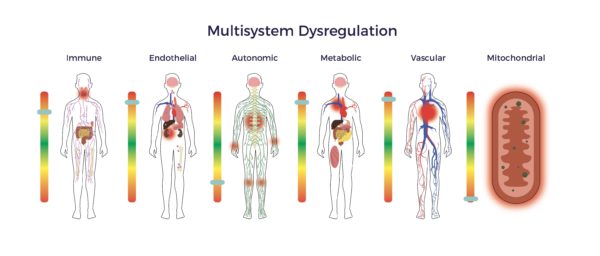

To solve for this, doctors prescribe patients drugs for each ailment or symptom, e.g., Sinemet for Parkinson’s, Ambien for sleep, steroids for arthritis, opioids for pain, and so forth.

Drug side effects include accelerating the decline in cognitive function.[8]
Dr. Armon Neel Jr. cautions that ten drug classes contribute to dementia progression.

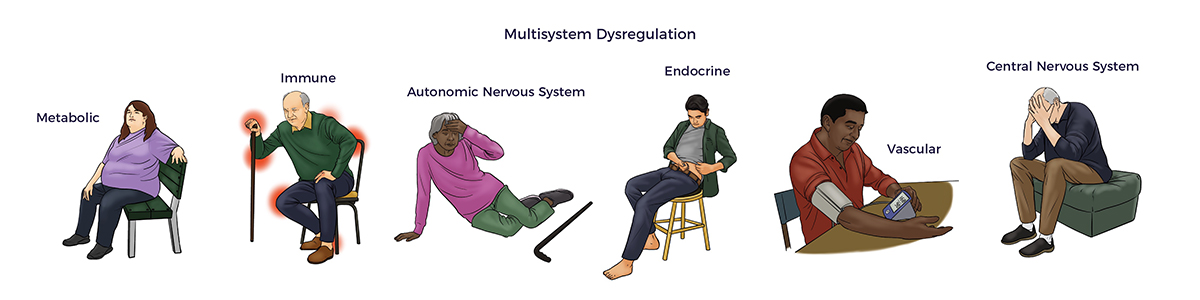
Multisystem dysregulation is a chicken and egg problem. Nearly all patients with brain degeneration live with multiple chronic conditions (co-morbidities).

Tim’s ADRCs – Miracle-Gro For His Brain
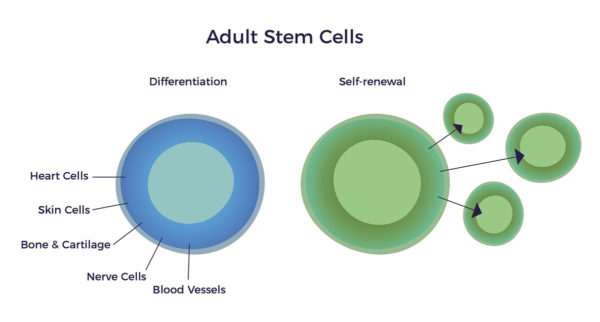
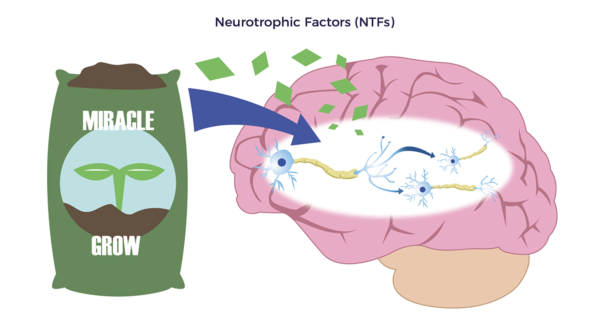
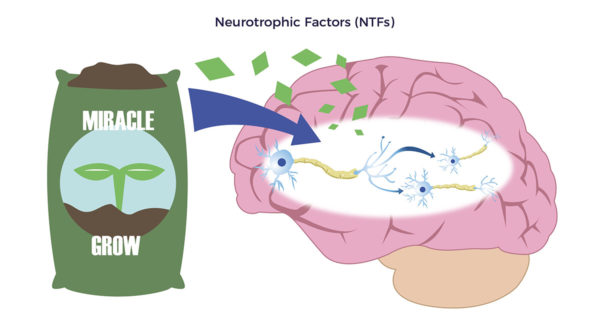
Miracle-Gro feeds your garden’s soil with the nutrients it needs to grow healthy roots, stems, petals, and leaves. And just as there are situations in which we fertilize a plant lacking vital nutrients, ADRCs secrete growth factors essential to the health of our aging brains, hearts, muscles, nerves, and so on. [9]  Growth factors (GFs) are a type of cytokine or healing molecule that act on other cells to stimulate growth and function.

One such growth factor group is “Neurotrophic factors (NTFs).” Neuro relating to nerve and trophic, from Ancient Greek trophikós, meaning “of food or nourishment.” In other words, NTFs feed our neurons and nerves with nutrients.

Brain-derived neurotrophic growth (BDNF) stimulates new brain cells, brain cell connections, and nerves. It also repairs the myelin sheathing surrounding the nerves.

It gets better: BDNF is anti-inflammatory and prevents programmed cell death (apoptosis) resulting from an injury or disease. [10] [11] [12] [13] [14]
Many benefits are associated with higher levels of BDNF, including improved mood, productivity, and memory. One 10-year study that tracked BDNF levels in adults found that those with low levels were twice as likely to develop dementia and Alzheimer’s than those with the highest levels.[15]
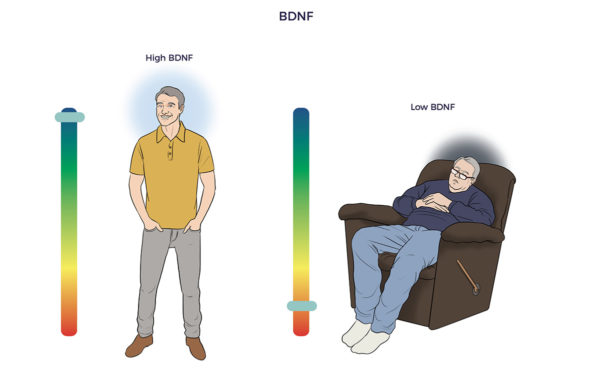
John Hopkins researchers developed a BDNF-blood test that could have predicted the severity of Ali’s head damage and how he would fare. Their study showed that patients with brain injuries have less than one-third of the BDNF as those with healthy brains.

The most severe TBIs had even lower levels- about 5% of normal. Moreover, patients with high levels of BDNF recovered from their injuries six months later. But symptoms lingered at follow-up in patients with the lowest levels of BDNF.[16]
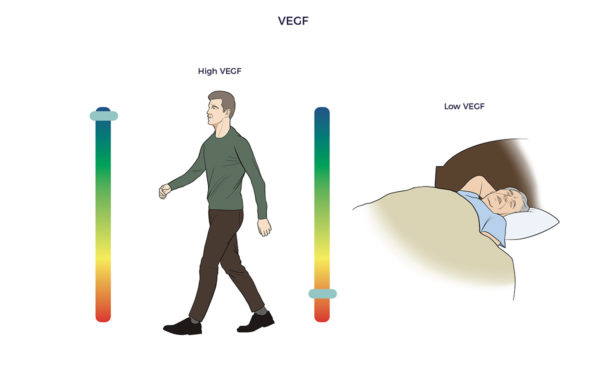
ADRCs also enrich the brain with vascular endothelial growth factor (VEGF). VEGF restores blood flow and reduces inflammation in withering tissues, blood vessels, and organs. One study found higher levels of VEGF in asymptomatic seniors who died with amyloid plaques compared to symptomatic Alzheimer’s patients.

Notably, ADRCs secrete dozens of other healing factors.[17]

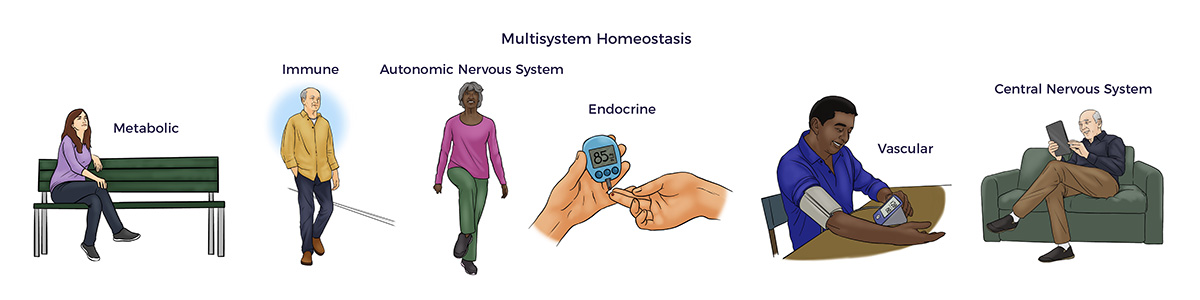
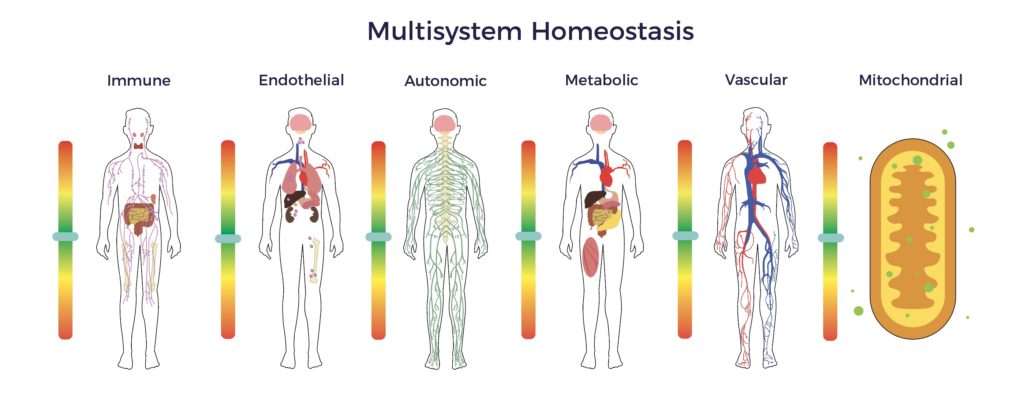
In combination, ADRCs restore multisystem balance or homeostasis – at the cellular, tissue, organ, and multisystem levels.
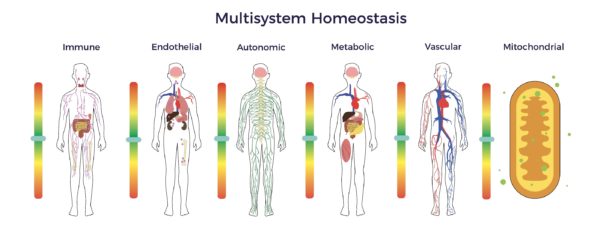
By the way, big pharma can’t discover a single molecule they can sell millions of copies of per year that can restore physiologic balance. Their drugs suppress the disease’s presumed- but often wrong -causes.

Thus, we believe Ali could have benefited from accessing his ADRCs. The medical literature supports it – and so does Tim’s powerful reversal of his symptoms. If only Ali had the Right to Try. [18] [19] [20] [21] [22] [23]

[1] Ledreux A, Pryhoda MK, Gorgens K, Shelburne K, Gilmore A, Linseman DA, Fleming H, Koza LA, Campbell J, Wolff A, Kelly JP, Margittai M, Davidson BS and Granholm A-C (2020) Assessment of Long-Term Effects of Sports-Related Concussions: Biological Mechanisms and Exosomal Biomarkers. Front. Neurosci. 14:761.

[2] Tarakad A, Jankovic J. Essential Tremor and Parkinson’s Disease: Exploring the Relationship. Tremor Other Hyperkinet Mov (N Y). 2019; 8:589. Published 2019 Jan 9.

[3] Ledreux A, Pryhoda MK, Gorgens K, Shelburne K, Gilmore A, Linseman DA, Fleming H, Koza LA, Campbell J, Wolff A, Kelly JP, Margittai M, Davidson BS and Granholm A-C (2020) Assessment of Long-Term Effects of Sports-Related Concussions: Biological Mechanisms and Exosomal Biomarkers. Front. Neurosci. 14:761.

[4] Lehman EJ, Hein MJ, Baron SL, Gersic CM. Neurodegenerative causes of death among retired National Football League players. Neurology. 2012 Sept 5 [Epub ahead of print].

[5] R. Jorge et al Major Depression Following Traumatic Brain Injury Arch Gen Psychiatry/Vol 61 Jan 2004

[6] D. Nampiaparampil   Prevalence of Chronic Pain After Traumatic Brain Injury A Systematic Review. JAMA.2008;300(6):711–719.

[7] Langston J W The Parkinson’s Complex: Parkinsonism Is Just the Tip of the Iceberg Annals of Neurology Vol 59 No 4 April 2006

[8] Ishii N et al. Polypharmacy Associated with Cognitive Decline in Newly Diagnosed Parkinson’s Disease: A Cross-Sectional Study Dement Geriatr Cogn Disord Extra 2019; 9:338–343

[9] A Caplan PhD MSCs: The Sentinel and Safe-Guards of Injury J. Cell. Physiol. 231: 1413–1416, 2016.

[10] Razavi, Shahnaz et al. “Neurotrophic Factors and Their Effects in the Treatment of Multiple Sclerosis.” Advanced Biomedical Research 4 (2015): 53. PMC. Web. 28 Sept. 2018.

[11] J. K. Huang et al Myelin Regeneration in Multiple Sclerosis: Targeting. Endogenous Stem Cells., The American Society for Experimental NeuroTherapeutics, Inc. 2011

[12] T Lopatina et al. (2011) Adipose-Derived Stem Cells Stimulate Regeneration of Peripheral Nerves: BDNF Secreted by These Cells Promotes Nerve Healing and Axon Growth De Novo. PLoS ONE 6(3): e178991

[13] S.  Seigo et al, Uncultured adipose-derived regenerative cells promote peripheral nerve regeneration, Journal of Orthopaedic Science, Volume 18, Issue 1,2013, Pages 145-151

[14] Xu et al Brain-derived neurotrophic factor reduces inflammation and hippocampal apoptosis in experimental Streptococcus pneumoniae meningitis Journal of Neuroinflammation (2017) 14:156

[15] Jiao SS, Shen LL, Zhu C, et al. Brain-derived neurotrophic factor protects against tau-related neurodegeneration of Alzheimer’s disease. Transl Psychiatry. 2016;6(10):e907.

[16] FK K. Korley et al Circulating Brain-Derived Neurotrophic Factor Has Diagnostic and Prognostic Value in Traumatic Brain Injury JOURNAL OF NEUROTRAUMA 33:215–225 (January 15, 2016)

[17] Hirose, Yujiro et al. Comparison of trophic factors secreted from human adipose-derived stromal vascular fraction with those from adipose-derived stromal/stem cells in the same individuals Cytotherapy, Volume 20, Issue 4, 589 – 591

[18] JK Fraser PhD and S. Kesten MD Autologous Adipose Derived Regenerative Cells: A platform for therapeutic applications Advanced Wound Healing Surgical Technology International XXIX

[19] C. Tate and C Case. Mesenchymal Stromal Cells to Treat Brain Injury. Advanced Topics in Neurological Disorders.

[20] S Dobrowolski and G Lepski. Stem Cells in Traumatic Brain Injury. American Journal of Neuroscience 4 (1): 13-24

[21]CS et al. Autologous bone marrow mononuclear cell therapy for severe traumatic brain injury in children. Neurosurgery 2011; 68: 588–600

[22] N Tajiri et al. Intravenous transplants of human adipose-derived stem cell protect the brain from traumatic brain injury-induced neurodegeneration and motor and cognitive impairments: cell graft biodistribution and soluble factors in young and aged rats. J Neurosci. 2014 Jan 1;34(1):313-26

[23] Sharma et al Cell therapy attempted as a novel approach for chronic traumatic brain injury – a pilot study SpringerPlus (2015) 4:26


AMBROSE Cell Therapy

Your Right to Try

Can something be done for Covid Long-Haulers?

Can something be done for Covid Long-Haulers?

Can something be done for Covid Long-Haulers?

After living with severe long-Covid symptoms and pre-existing health conditions, Brian exercised his Right to Try AMBROSE Cell Therapy in November 2021. He says AMBROSE has had “a massive effect on my health and quality of life.” Brian adds, nine months out, “I am doing things I couldn’t do a month ago.”

Remarkably, Brian’s many benefits occurred despite ongoing business stress and the difficult loss of two family members.

BackgroundSince December 2019, SARS coronavirus 2 (SARS-CoV-2) has spread like wildfire across the globe.  Unlike the seasonal flu or cold, COVID-19 can attack all body systems and multiple organs.
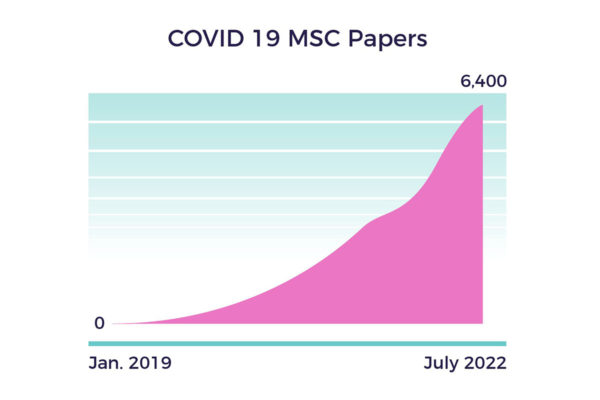
In response to the virus’ scorched earth capabilities, stem cell researchers worldwide have collaborated to improve outcomes for high-risk Covid patients and long-haulers. [1]

The researchers drew from over 200,000 published papers on Mesenchymal Stem Cells (MSCs). By July 2022, their urgency resulted in 6,400 articles or around 12 daily.

The in-human MSC studies included Covid-induced:
  • Acute respiratory distress syndrome (ARDS) [2]
  • Multisystem inflammatory syndrome in children [3]
  • Multi-organ disease, including sudden cardiac arrest [4]
  • COVID-19 pneumonia in April 2020. [5]

Dr. Pietro Gentile and others focused their research on adipose-derived stem cells (ADSCs) and ADRCs.  [6] [7] [8] [9]

Can ADRCs help Covid Long-Haulers?

Most promising for Brian, his long-Covid symptoms intersected with those from hypermobility, concussions, renal failure, Lyme Disease, and post-chemo side effects.

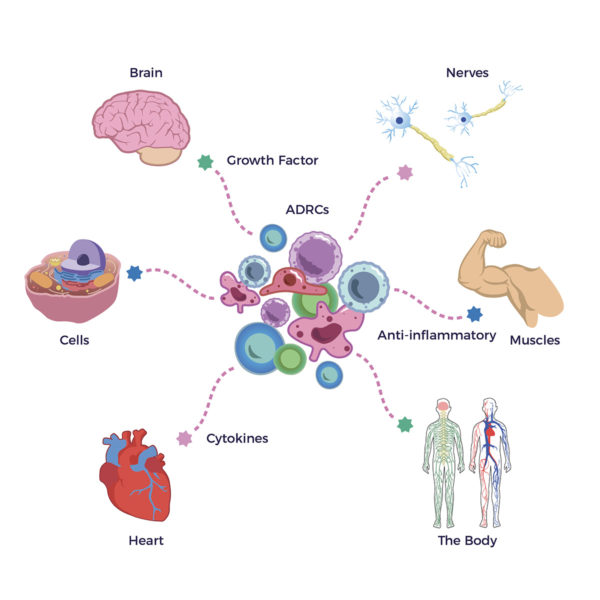
In response to one or more of these insults, our ADRCs secrete growth factors (GFs) and anti-inflammatory signaling proteins or cytokines essential to our brains, hearts, muscles, nerves, cells, and body health in general.

We share more on GFs and cytokines in Brian’s story that follows.

Ambrose patients Trish, Wouter, Kathy, and other patients with brain fog, fatigue, joint pain, and so on responded to ADRC-based therapy.  Therefore, it made sense for Brian to try AMBROSE Cell Therapy.

Brian’s Story
In December 2020, Brian’s doctor admitted him to the Cedar-Sinai ICU with COVID-19, returning home as a Covid long-hauler after two weeks.

After an introductory call with CEO Matt Feshbach, AMBROSE provided an educational MD consult, overview articles, and peer-reviewed papers supporting the safety and potential effectiveness of the therapy for long-Covid and the other conditions affecting him. Brian said,” (Matt) answered my questions. I had sufficient understanding to move forward.”

Covid Long-Hauler Symptoms
Brian experienced classic long-hauler symptoms: brain fog, chronic fatigue, and emotional volatility. As he summarized, “Most of 2021 was a lost year.”
He started to notice benefits shortly after his AMBROSE treatment. “After about a month, I saw a massive improvement in my mental clarity and energy. Business associates said they noticed the difference too. I didn’t realize how bad the fatigue was until I regained my strength.”

Supporting Brian’s statements, ADRCs release “Neurotrophic factors (NTFs),” Neuro relating to nerve and trophic, from Ancient Greek trophikós, meaning” of food or nourishment.”  NTFs, through multiple mechanisms, reduce neuroinflammation and stimulate the development of new brain cells, brain cell connections, and nerves. [10] [11]
Just as fertilizers keep plants healthy and growing, neurotrophic factors work like Miracle Grow for the brain.

Brian’s restored energy and mental clarity make sense in light of the above.

Vasculitis
Covid left Brian with debilitating inflamed blood vessels and swelling in both legs, or vasculitis, an autoimmune condition. He also complained of constant numbness and tingling in both legs (neuropathy). The right leg was worse than the left.


“My vasculitis and neuropathy went away shortly following the treatment.”

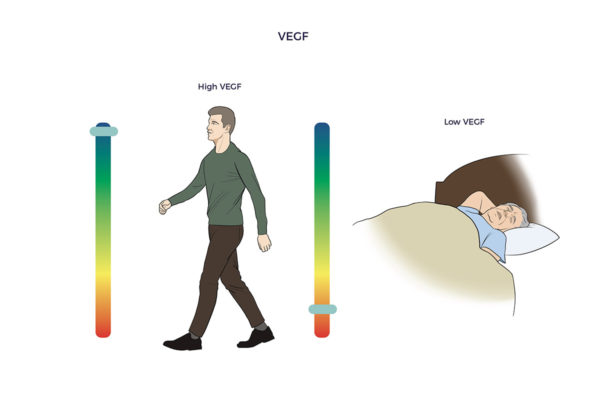
In addition to the NTFs, ADRCs secrete Vascular Endothelial Growth Factor (VEGF). VEGF improves circulation, reduces inflammation, and stimulates the growth of new blood vessels.

Here again, it makes sense that Brian’s swollen blood vessels and nerves calmed down. And an abundance of literature supports Brian’s subjective experience. [12] [13]

And back to Brian’s brain: VEGF reduces neuroinflammation and improves blood flow in the brain. In contrast, neuroinflammation and lack of blood flow in the brain cause chronic fatigue, brain fog, and memory issues. [14] [15]

Pre-Existing Conditions
Brian entered the hospital with a galaxy of pre-existing conditions that had failed to improve with surgeries, drugs, and devices.

Before the pandemic, Brian lived with:

  • Obesity
  • Arthritis in his lower back, shoulders, hips, and knees
  • Asthma
  • Fractured ribs
  • Osteopenia (an early stage of osteoporosis) and
  • A mildly enlarged heart and shortness of breath

In summary, Brian suffered from multisystem dysregulation.

His medications included Prednisone 30-mg daily, Singulair, Symbicort, and Spiriva for Asthma. Ambien for sleep.

Can ADRCs help Covid long-haulers with pre-existing conditions?
In 2016 The California Institute of Regenerative Medicine (CIRM) contributed funding to two review papers that supported ADRC-based treatment for Brian’s chronic illnesses. Further, preeminent researchers from Tulane University and other respected research institutions have continued the growing support for ADRCs’ potential to treat multiple diseases. [16] [17] [18]

Obesity
Brian has struggled with his weight since a young age. “I have probably lost 300 lbs. throughout my life. I tried bariatric surgery in 2007 but gained the weight back.”

“Since my treatment, I have dropped about 50 lbs. and have maintained my weight within a lower range with a less restrictive diet for the first time.”

In 1994, super-sleuth Jeffrey M. Friedman of Rockefeller University established fat as an endocrine organ. In simple terms, he discovered adipose cells secrete hormones that regulate weight gain. His insight explains Brian’s improved metabolism and fat burning following his cell therapy treatment. [19] [20]

Wear, Tear, and Trauma
Brian played football in high school, resulting in some head traumas. He was involved in several major motor vehicle accidents in his early 20s. He went unconscious twice. “They took me to the hospital several times; it was pretty bad.”

Football, basketball, baseball, skiing, and excess weight was not kind to Brian’s joints either.

  • Three right-knee operations failed, leaving both knees painful.
  • He experienced degenerative arthritis in his shoulders.
  • His right and left hips were arthritic as well.

Steroid injections in the affected joints failed to give Brian relief. He tried bone-marrow stem cell injections for his shoulders, but that “didn’t work at all.”

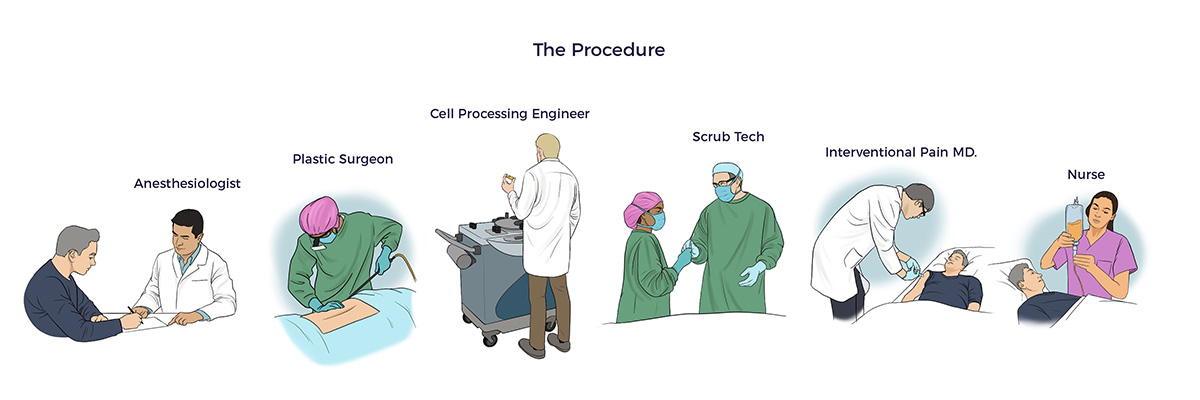
Ambrose’s interventional pain specialist developed a personalized treatment plan based on a Master Protocol. He delivered 22 injections of PRP-enriched micronized fat into Brian’s painful joints.

A month out, his PT said, “Brian’s weight-bearing tolerance and conditioning are improving. He’s doing great.”

Eight months out, Brian shared, “My shoulder, hips, and knees feel good. My back is fine.”

Asthma
Brian developed asthma in his 40s after spending a month in China on business. Before his stem cell treatment, he used three inhalers and took 30 mg of prednisone daily.

Nine months after Brian’s AMBROSE treatment, he says, “I have lowered my daily prednisone dose to 10 mg and occasionally miss taking it without an asthma flare. I significantly reduced my use of inhalers, too.”

Fractured Ribs
An asthma-induced coughing attack fractured four ribs on March 1, 2018. After reviewing Brian’s x-rays, his orthopedist told him he could not repair the ribs. Additionally, Brian had an underlying diagnosis of osteopenia, a condition involving reduced bone mass.

Studies showed that ADRCs stimulate bone healing. [21]

The Ambrose physician injected the fractured ribs. Several months later, Brian reported, “My ribs feel like they healed. That is impressive” To be clear, he still experiences mild discomfort, “but nothing like it was before.”

Mildly Enlarged Heart
A 2018 cardiac workup revealed Brian had a mildly enlarged heart and shortness of breath.
His cardiologist and PT agree the shortness of breath is no longer evident.

The PRECISE cardiac cell therapy study demonstrated significant improvements in endurance, thus supporting Brian’s doctor’s observations. [22] A new cardiac workup is in order.

Multisystem Balance Restored
Brian’s patient-reported outcome demonstrates the potential to restore multisystem homeostasis (balance) by utilizing his ADRCs.

Recommending AMBROSE to Family and Friends

“I have recommended Ambrose to my mother and best friend. It makes sense for them to try it too. Both have arthritic joints, back pain, and other medical issues.”


[1] Yasamineh et al. Spotlight on therapeutic efficiency of mesenchymal stem cells in viral infections with a focus on COVID-19 Stem Cell Research & Therapy (2022) 13:257
[2] Wick K et al. Mesenchymal stromal cells reduce evidence of lung injury in patients with ARDS JCI Insight 2021;6(11):e148983
[3] Ross Eckard A, Borow KM, Mack EH, Burke E, Atz AM. Remestemcel-L therapy for
COVID-19-associated multisystem inflammatory syndrome in children. Pediatrics. 2021
[4] Yilmaz R et al. Mesenchymal stem cells treatment in COVID-19 patient with multi-organ involvement Bratisl Med J 2020; 121 (12) 847-852
[5] Zeng et al. Transplantation of ACE2- Mesenchymal Stem Cells Improves the Outcome of Patients with COVID-19 Pneumonia Aging & Disease Volume 11 Number 2; 216-228, April 2020
[6] Stromal Vascular Fraction or SVF is the generic term for clinical grade adipose-derived regenerative cells.
[7] Pietro Gentile, Aris Sterodimas. Adipose Stem Cells (ASCs) and Stromal Vascular Fraction (SVF) as a Potential Therapy in Combating (COVID-19)-Disease. Aging and disease. 2020, 11(3): 465-469
[8] Alexander RW. (2020) Overview of COVID-19 Lung Damage Clinical Trial Using Cellular
Stromal Vascular Fraction (cSVF) and Functional Respiratory Imaging (FRI) Analysis of Pulmonary Injury
& Post-Viral (SARS-CoV-2) Adult Respiratory Distress Syndrome (ARDS). Stem Cell Res. 1(1)-1-19.
[9] Sanchez-Guijo F et al. Adipose-derived mesenchymal stromal cells for the treatment of patients with severe SARS-CoV-2 pneumonia requiring mechanical ventilation. A proof of concept study EClinical Medicine 000 (2020) 100454
[10] S. Seigo et al, Uncultured adipose-derived regenerative cells promote peripheral nerve regeneration, Journal of Orthopaedic Science, Volume 18, Issue 1,2013, Pages 145-151
[11] Xu et al Brain-derived neurotrophic factor reduces inflammation and hippocampal apoptosis in experimental Streptococcus pneumoniae meningitis Journal of Neuroinflammation (2017) 14:156
[12] Liao L. Mesenchymal stem cell and hematopoietic stem cell transplantation for vasculitis. Vasc Invest Ther 2020; 3:88‐93.
[13] Jahangir S et al. New advanced therapy medicinal products in treatment of autoimmune diseases Editor(s): Nima Rezaei, In Translational Immunology, Translational Autoimmunity, Academic Press, Volume 2, 2022, Pages 319 359,
[14] Skok M. Mesenchymal stem cells as a potential therapeutic tool to cure cognitive impairment caused by neuroinflammation. World J Stem Cells 2021; 13(8): 1072-1083
[15] J Rosenstein, J Krum & C Ruhrberg VEGF in the nervous system Organogenesis 6:2, 107-114; April/May/June 2010; © 2010 Landes Bioscience
[16] Nguyen A et al. Stromal vascular fraction: A regenerative reality? Part 1: Current concepts and review of the literature Journal of Plastic, Reconstructive & Aesthetic Surgery (2016) 69, 170e179
[17] Guo J et al. Stromal vascular fraction: A regenerative reality? Part 2: Mechanisms of regenerative action Journal of Plastic, Reconstructive & Aesthetic Surgery (2016) 69, 180e188
[18] Al-Ghadban S, Artiles M, Bunnell BA. Adipose Stem Cells in Regenerative Medicine: Looking Forward. Front Bioeng Biotechnol. 2022; 9:837464. Published 2022 Jan 13.
[19] Zhang, Y; Proenca, R; Maffei, M; Barone, M; Leopold, L; Friedman, JM (December 1994). “Positional cloning of the mouse obese gene and its human homologue”. Nature. 1994 (372): 425–432
[20] Zuccarini, M et al Adipose Stromal/Stem Cell-Derived Extracellular Vesicles: Potential Next-Generation Anti-Obesity Agents. Int. J. Mol. Sci.
2022, 23, 1543.
[21] Saxer F et al. Implantation of Stromal Vascular Fraction Progenitors At Bone Fracture Sites: From A Rat Model To A First-In-Man Study STEM CELLS 2016; 00:00-00
[22] Perin E et al., Adipose-derived regenerative cells in patients with ischemic cardiomyopathy: The PRECISE Trial Am Heart J 2014;168:88-95.e2.

AMBROSE Cell Therapy

Your Right to Try

A Golden Era of Cell-Assisted Aging

A Golden Era of Cell-Assisted Aging

A Golden Era of Cell-Assisted Aging

Back to the Future

For Mary, aging was not dying – it was disability; A transformative therapy, using her own Adipose-Derived Regenerative Cells (ADRCs), brought her Back to the Future.

In the summer of 2014, Mary’s doctor admitted her to the Cleveland Clinic ICU. After two weeks, the doctors sent her home with but one recommendation: Prepare for hospice.

Several months later, AMBROSE Cell Therapy’s predecessor group treated Mary with a novel ADRC-based protocol. Seven years after that single treatment, Mary celebrated her 93rd birthday with friends.

In 2021, Mary lived independently, her Parkinson’s symptoms were mild compared to her baseline, and her mood was upbeat. [1]  She exercised at the gym four days per week. Her back pain and sciatica had long since resolved.

Science Fiction Becomes Reality
Perhaps the renowned science fiction author Ray Bradbury foretold Mary’s outcome in The Illustrated Man, “She went back to the future,’ he said. ‘I mean it. She was an old woman in a little house in the middle of Wisconsin here, somewhere not far from this place. An old witch who looked a thousand years old in one moment and twenty years old the next, but she said she could travel in time. I laughed. Now I know better.’ “

Mary’s remarkable turnaround turned sci-fi into reality, as often happens with that genre. But how did Mary’s ADRCs help her time travel, particularly with the odds stacked against her?

Mary’s Story
By 86, Parkinson’s had disabled, depressed, and hurt Mary. Tremors prevented her from using a fork and knife.

She lived with chronic back pain and sciatica after a fall that fractured her back in three places. Mary relied on 24/7 care.

In May of 2014, Mary attended her granddaughter’s wedding in a wheelchair. Per her primary care physician, “All the guests were commenting on her deteriorating health and how they did not expect her to survive much longer.”

After spending two weeks in the Cleveland Clinic ICU, the doctors told Mary to get her affairs in order. All this left her depressed with thoughts of suicide.

In October 2014, Ambrose’s predecessor group treated Mary with a novel ADRC-based protocol, which sparked her Comeback to the Future. Seven years after that single treatment, Mary celebrated her 93rd birthday with friends.
She lived independently, her Parkinson’s symptoms were mild compared to her baseline, and her mood was upbeat. Mary walked on the treadmill and worked out at the gym four days per week. Her back pain and sciatica had long since resolved.

Living to 93 is one thing; it’s another to be active and enjoy life despite all odds.

Aging’s Dismal Future
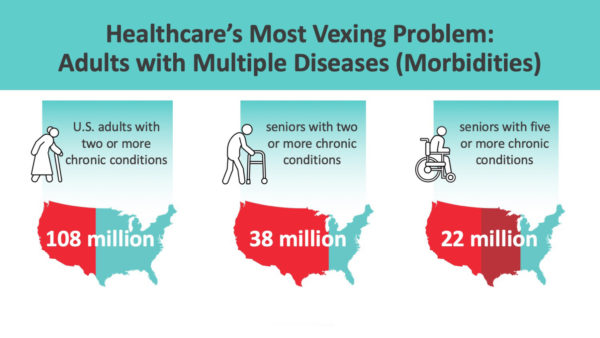
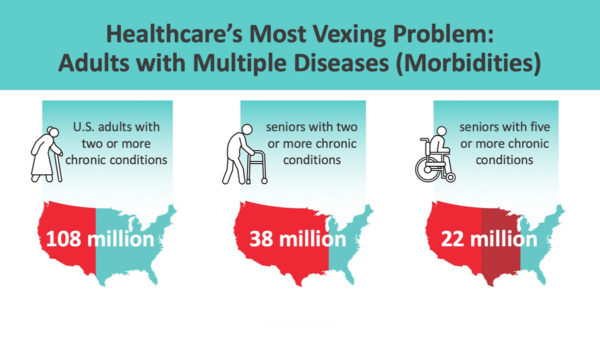
Until cell therapy sparked Mary’s recovery, she shared a dismal future with over 100 million adults. Four out of ten adults live with two or more chronic diseases.

As we age, the situation becomes dire: The average senior sees seven doctors and takes seven meds per year.

Connecting the Dots
At the time of Mary’s treatment, stem cell researchers had not yet connected the common factors of age-related conditions with the cellular mechanisms that enabled Mary’s remarkable reversal of symptoms, function, and quality of life. The secret to going Back to the Future lies in that relationship.

Coming Back to the Future, we now understand that Mary’s ADRCs abided by the laws of nature. But how? Centuries-long research held the clue. And new-age science and technology unraveled the mystery. More on that later, first, let’s catch up with the past.

Back to Nature – Physiology, and Balance
Going Back to the Future requires going back to basics, starting with physiology. Physiology traces its roots to ancient India, Egypt, and Greece.

  • Hippocrates, the Father of Medicine, played a crucial role in introducing the Four Humors (bodily fluids). His fifth-century BC treatise, The Nature of Man, defined good health as the balance and mixture of the humors while their imbalance and separation caused disease.
  • Jean Fernel (1497-1558), a French physician, introduced the term “physiology,” from Ancient Greek, meaning “study of nature, origins.” In other words, physiology refers to the body’s natural processes, functions, and systems. He published his book The Natural Part of Medicine in 1542.
  • In the 1870s, Claude Bernard, a French physiologist, described how complex organisms must maintain balance in their internal environment, or “milieu intérieur,“to lead a “free and independent life” in the world beyond.
  • Fifty years later, physiologist Walter Cannon coined the term homeostasis, expanding on Hippocrates’, Fernel’s, and Bernard’s work. From the Greek words for “same” and “steady,” homeostasis refers to the physiologic balance necessary for survival.
  • In 1948, biologist Claude Shannon, Ph.D., wrote the Magna Carta of the Information Age, Information Theory. Here, Shannon bridged DNA signaling processes to digital communications. [2] His paper ignited the technology revolution. In other words, our iPhones, computers, and the Internet evolved from cellular crosstalk.
  • It took another six decades for Arnold Caplan, Ph.D., a stem cell researcher at Case Western University, to connect physiology, homeostasis, and Information Theory to stem cell biology.

Big Pharma’s Profitable Failure
In contrast, Big Pharma ignores these fundamentals in favor of drugs, many with risks than can outweigh the benefits. For example, Dr. Armon Neel Jr. cautions that ten drug classes can cause or contribute to memory loss, brain fog, and fatigue.

Conventional medicine adheres to Big Pharma’s “one drug, one disease” model. Here, doctors prescribe pharmaceuticals that suppress the primary factor causing a disease or a symptom. This approach has done little to improve patients” healthspan with age-related diseases. And it did not work for Mary either.

 In Mary’s case, she was taking Sinemet for tremors, Lyrica for pain, and Cortisone shots for sciatica – at a minimum. Drug companies make a lot of money from multiple drug prescriptions (polypharmacy) – but Mary’s health did not profit to the same degree, e.g., she talked of suicide, a known side-effect of both Lyrica and Sinemet.

Mary’s Comeback
As her daughter said 18 months after Mary’s treatment, “For her back, the results were incredible. She had two fractures in her lower lumbar. A lot of people never would have gotten out of bed, but she’s 87, and we call her the comeback kid. She’s up at the gym almost every day now with her trainer, who sometimes has to ask her to tone it down, so she doesn’t over-exert herself!”

“Beyond that, now she is walking very straight and isn’t shuffling her feet. Occasionally when she’s tired, she’ll veer off a little, but she’s not using a walker or a cane. She is doing really, really well, and a lot of this is due to the stem cell therapy.

Is Mary’s story a placebo effect? It all sounds too good to be true, but other Patient-Reported Outcomes demonstrate Mary’s benefits are not unique to her.

Bridging the Gap

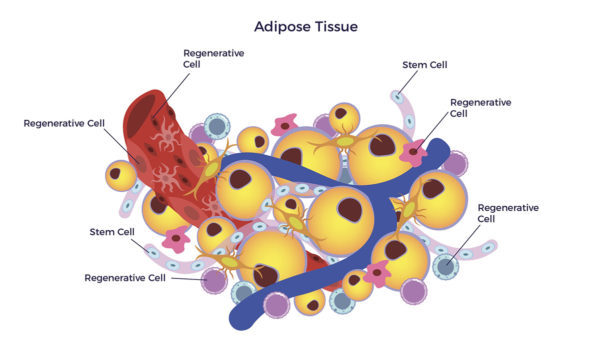
  • In the mid-1960s, Martin Rodbell, Nobel Laureate for Physiology or Medicine, isolated a mixed population of regenerative cells in fat or adipose tissue called stromal vascular fraction (SVF). Stroma means connective tissue (fat). Fraction is the cellular fraction liberated from the outer lining of the vessels intermingled in the fat.
  • In 1991, Arnold Caplan, Ph.D., envisioned “the emergence of a new therapeutic paradigm, “Self-Cell Repair”. Dr. Caplan postulated that a person’s adult stem cells, which he named mesenchymal stem cells (MSCs), could be used to repair diseased tissues and organs.
  • Ten years later, UCLA researchers Patricia Zuk et al. discovered the most accessible, abundant, and potent source of MSCs: Adipose Tissue. Zuk’s group bridged the gap between the age-old science of physiology and the new-age medicine of ADRCs.
  • Ten years after Zuk’s lab discovery, Dr. Caplan renamed MSCs “medicinal signaling cells,” connecting physiology, homeostasis, DNA signaling, and stem cell biology.
  • ADRCs contain DNA in each cell’s nucleus. Thus, they adhere to Caplan’s Medicinal Signaling Cell framework.

  • In 2012, Dr. James Willerson and Dr. Emerson Perin from Texas Heart Institute published Buying New Soul. Here, they proposed adipose tissue as the best source of adult stem and regenerative cells – and connected Bradbury’s Back to the Future with ADRCs’ potency late in life. In other words, fatty tissue protects these cells from dreaded stem cell exhaustion.

Notably, over the past 22 years, investigators have published over 85,000 papers discussing adipose-derived stem cells (ADSCs). That is an average of 11 new publications per day. Most impressive, the publishing rate has accelerated to 36 papers per day, nearly four times the historical average.

A Golden Era of Cell-Assisted Aging?
Aging constitutes a sudden or general onset of multiple physiologic imbalances or multisystem dysregulation. Mary’s symptoms were a good example of this.

In 2006, Dr. William Langston, the Michael J. Fox Foundation’s first Chief Science Officer, published The Parkinson’s Complex: Parkinsonism Is Just the Tip of the Iceberg. [3] In short, Dr. Langston’s seminal paper stated there is more to PD than the loss of dopamine-producing neurons in the brain.

Instead, Parkinsonism involves multisystem breakdowns. Therefore, he stated, “Rather, we must deal with all aspects of the disease if we are to modify its progress in a way that truly enhances the lives of our patients over the long term.“

Likewise, researchers connect negative systemic influences with heart failure, kidney disease, Alzheimer’s, diabetes, and so on.

Succinctly, as we age, our cells, tissues, organs, and systems lose harmony. [4] [5] [6]  Instead, multiple conductors direct the orchestra according to their respective interpretations of the score.[7] [8] [9] [10] [11]

In other words, our immune, vascular, nervous, and other systems give dissonant instructions to our cells, tissue, and organs. Simply put, multisystem disharmony is the overarching factor underlying Mary’s symptoms.  [12] [13] [14] [15] [16]

After her one-time treatment, Mary’s ADRCs restored physiologic harmony.

In scientific terms, her restorative cells secreted hundreds of healing, or trophic factors, that signaled the resident cells to resume playing according to her musical score.

Put another way, Dr. Caplan’s Medicinal Signaling Cell framework performed better than he hypothesized. The cellular cross talk between the MSCs and the resident cells restored multisystem homeostasis.

In the real world, Mary’s mood, energy, motor control, balance, and pain score remain improved for more than seven years.
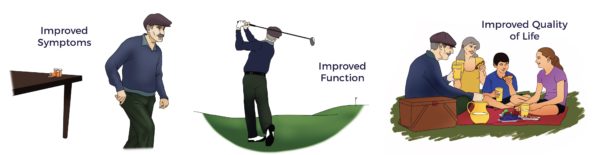
Further, Mary’s outcome validated Dr. Langston’s 2006 hypothesis. Most important, Mary, her friends, and her family enjoyed her Comeback to the Future.

[1] Based on information provided by Mary, her primary care, family, and friends. Medical records are not available.

[2] Schneider T A brief review of molecular information theory Nano Commun Netw. 2010 September; 1(3): 173–180

[3] Langston J W The Parkinson’s Complex: Parkinsonism Is Just the Tip of the Iceberg Annals of Neurology Vol 59 No 4 April 2006

[4] Takuya Kishi Heart failure as an autonomic nervous system dysfunction Journal of Cardiology (2012) 59, 117—122

[5] Sági B et al The prognostic role of heart rate recovery after exercise and metabolic syndrome in IgA nephropathy BMC Nephrology (2021) 22:390

[6] McCaulley M and Grush K Alzheimer’s Disease: Exploring the Role of Inflammation and Implications for Treatment International Journal of Alzheimer’s Disease Volume 2015, Article ID 515248,

[7] Kelleher R, Soiza R Evidence of endothelial dysfunction in the development of Alzheimer’s disease: Is Alzheimer’s a vascular disorder? Am J Cardiovasc Dis 2013;3(4):197-226

[8] Dantzer R. Neuroimmune Interactions: From the Brain to the Immune System and Vice Versa. Physiol Rev. 2018;98(1):477-504.

[9] Amiya E MD PHD et al The Relationship between Vascular Function and the Autonomic Nervous System Ann Vasc Dis Vol. 7, No. 2; 2014; pp 109–119 Online Month May 16, 2014

[10] Tracey K The inflammatory reflex Nature Vol 420 19/26 December 2002

[11] Simora N et al. The Role of the Immune System in Metabolic Health and Disease Cell Metabolism 25, March 7, 2017

[12] Kelleher R, Soiza R  Evidence of endothelial dysfunction in the development of Alzheimer’s disease: Is Alzheimer’s a vascular disorder? Am J Cardiovasc Dis 2013;3(4):197-226

[13] Dantzer R. Neuroimmune Interactions: From the Brain to the Immune System and Vice Versa. Physiol Rev. 2018;98(1):477-504.

[14] Amiya E MD PHD et al The Relationship between Vascular Function and the Autonomic Nervous System Ann Vasc Dis Vol. 7, No. 2; 2014; pp 109–119 Online Month May 16, 2014

[15] Tracey K The inflammatory reflex Nature Vol 420 19/26 December 2002

[16] Simora N et al. The Role of the Immune System in Metabolic Health and Disease Cell Metabolism 25, March 7, 2017

AMBROSE Cell Therapy

Your Right to Try

Realistic Expectations and Optimizing Your Outcome

Realistic Expectations and Optimizing Your Outcome

Realistic Expectations and Optimizing Your Outcome

It remains obvious that lifestyle contributes to health or disease. Excessive work, being sedentary, smoking, substance abuse, a poor diet, unhealthy relationships, etc., are associated with poor health.

Therefore, patients who take responsibility for their overall health and outcome are more likely to super-respond to their cell therapy.

On the opposite side of the coin, ignoring the basics of health and wellness should mute your expectations. Your outcome will be better to the degree that you contribute to the repair process.

FAQs

When should I begin exercise?
You may start walking and light exercise within a week or two of your procedure, depending upon when you feel up to it.

Patients should begin exercising at 25% of their normal level at about four weeks out. You may increase that by 25% every two weeks. In other words, most patients take a little more than two months to return to playing golf, tennis, yoga or working out.

You should take your time before resuming sports known to stress the musculoskeletal system. Your body will tell you if you are doing too much too soon or can do more than the formula above.

The repair process takes time. Exercise helps it but rushing back into sports works against that process. The needed period varies from person to person. Patience remains a virtue.

When will I begin to experience benefits?
Every patient is unique; therefore, their path of improvement differs. Bearing that in mind, most patients experience notable benefits between four and six weeks.
Because ADRCs are regenerative and restorative, they continue to do their jobs for months and even years. Many patients say their rate of benefit accelerated over time.

What to expect when?
No two patients have responded the same, yet AMBROSE’s Patient-Reported Outcomes suggest a pattern:

  1. Patients feel an emotional lift. They express this as more energy, happier, equanimity, a sense of well-being, and mental clarity.
  2. Pain begins to subside, and function starts to improve.
  3. They become more active.

Is stem cell therapy a cure?
A cure implies one never experiences a sign or symptom of a disease again. This expectation is unrealistic. In contrast, Ambrose Cell Therapy aims to improve symptoms, function, and quality of life.

Who benefits the most?
Patients who adopt or continue common sense diet, exercise, and lifestyle practices benefit the most from cell therapy.
Notably, Ambrose can eliminate the requirement for extreme diets, excessive supplements, regular chiropractic adjustments, and so forth.
From a different angle, people who failed to respond to PT or other conservative modes of therapy before AMBROSE often do so after their treatment. Published studies support this potential benefit.

What causes a flare?
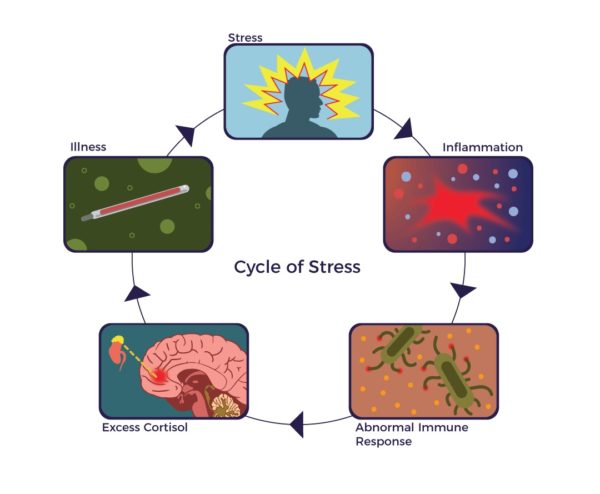
Levels of physical or psychological stress exceeding what an individual can tolerate fight with the healing process.

For example:

  • Some exercises aggravate back pain, e.g., crunches, the treadmill, and some stretches. It is different for everybody.
  • The same holds for shoulders, hips, knees, and so forth. You may find eliminating a particular exercise, dialing back the frequency or intensity, or improving your form resolves the flare.
  • Inactivity and overdoing exercise cause relapses or lack of response in the first place.
  • Dementia, Parkinson’s, MS, and other neurologic conditions lower tolerance for psychological and physical stress. Travel, work, large gatherings, and negativity may be too much for individuals living with these diseases. Thus, patients and their caregivers should not expect to travel, work, and socialize as they did before the onset of their condition. As symptoms subside, the goal is to return to activities with family and friends, sports, and work as appropriate for them.
  • Sometimes caregivers over-care for the family member. They bring them to multiple healthcare providers, restrict their diets, overdo nutritional supplements, and so on. Despite one’s best intentions, this approach adds stress. Instead, the best therapies are being with family and friends and doing enjoyable, relaxing activities.

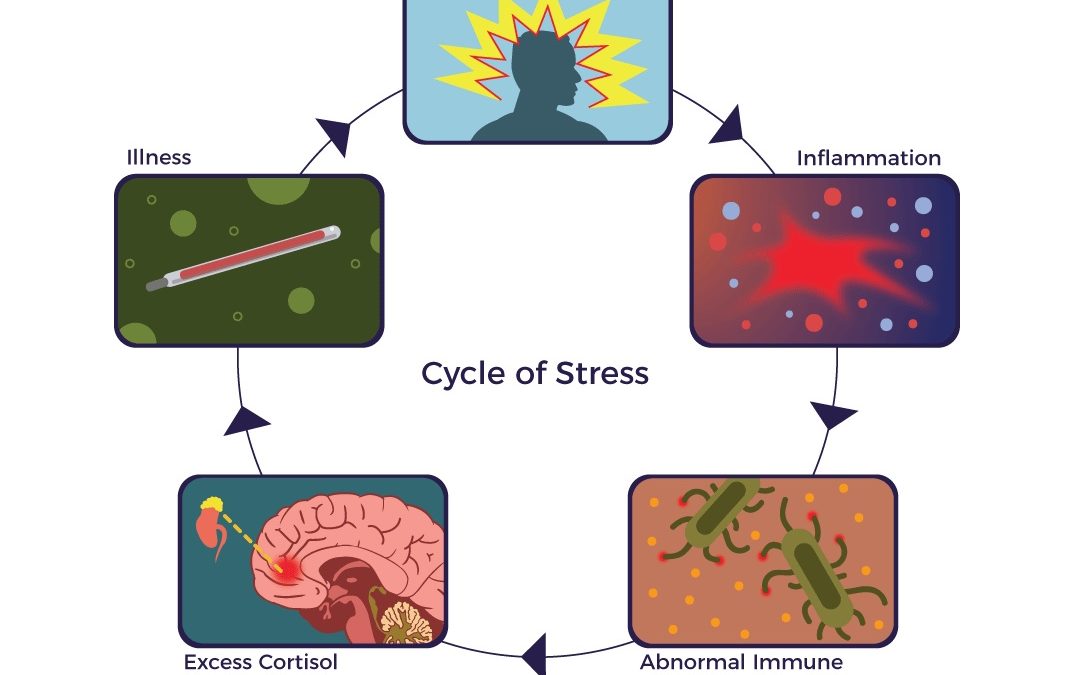
Improving Cell Therapy Outcomes explains the cycle of stress in more detail.

In summary, listen to your body and manage your activities accordingly. As the body becomes healthier, you can do more. On the other side of the coin, if specific exercises cause pain or other symptoms, it is essential to identify the triggers and modify what you are doing.

AMBROSE Cell Therapy

Your Right to Try

Tony Robbin’s Life Force Stem Cell Discussion Review

Tony Robbin’s Life Force Stem Cell Discussion Review

Tony Robbin’s Life Force Stem Cell Discussion Review

“After so many years of agony from my spinal stenosis, now I was standing straight and strong without an ounce of pain in my back. It felt supple and free, better than it had in decades. You know that expression, I felt like a brand-new person? Without exaggeration, that new person was me. Six years later, my shoulder is still perfect, with full range of motion. I don’t baby it; to be honest[…]” Life Force Tony Robbins, Peter Diamandis MD, and Robert Hariri MD

Tony Robbins wrote Life Force so we could be the CEOs of our health. He brings stem cell therapy to the front of the stage with his “brand-new person” account of his stem cell treatment in Panama. He tells a larger-than-life story because, well, that is Tony.

As to the science, Tony relies on well-respected experts (with whom he invests) for his “facts.” However, his stem cell explanation suffers from what behavioral finance gurus call “cognitive bias” (A. Tversky and D. Kahneman 1972).

Why Our Review?
This review separates fact from bias and real-world outcomes from unrealistic expectations. Further, we reconstruct Tony’s inspiring yet ambiguous narrative into a clarifying before-during-and-after timeline.

We presume that Tony benefited from cell therapy. Stem cells are effective in treating the conditions from which he suffered. It is just hard to know how much, for how long, and why. In Chapter 18, Tony dropped a subtle bomb on his born-again in Panama story: He did another treatment to handle the “challenges” related to the Panama treatment discussed in Chapter 2. More on that in a moment, first this review’s purpose.

Realistic Expectations
Our review aims to set realistic expectations and empower patients to make an informed choice regarding stem cell therapy. As Warren Buffett once counseled a CEO, “The way to have a happy marriage is to marry someone with low expectations.” Better said, it is best to set expectations cell therapy can meet or beat. Claims of immediate miracle cures do not help anyone.

Unfortunately, Tony’s too incredible to be believed stem cell miracle – in less than 72 hours- may set people up for disappointment. Stem cell therapy doesn’t take effect like a pain killer – at least for most people.

To be clear, Tony, Trish, and many other AMBROSE Cell Therapy patients report sustained benefits from a single treatment. But they improved for months or even years before they plateaued.

With all that said, we applaud Tony’s stem cell advocacy. He gives hope to 10’s of millions of people living with debilitating conditions unsatisfied with conventional and integrative medicine.

Back to Tony’s Story
Tony’s story begins: “I have to admit, I was acting more like a 14-year-old at the time, tearing down a mountain in Sun Valley, Idaho, on my snowboard. It went horribly wrong, and I fell with a bone-rattling force that annihilated my shoulder.

It turned out that I’d torn my rotator cuff, the set of tendons and muscles connecting the upper arm to the shoulder. Over the years, I’d dealt with lots of pain. This hurt so brutally that I didn’t know what to do with myself. On a scale of one to ten, I’d award this pain a score of 9.9!    My nerves were on fire. Deep breaths even hurt. Over the next two nights, I slept a grand total of two hours.” Ouch.

The melodrama continued. More on that in a moment, first let us fact-check Tony’s science presentation.

Fat Fact-checking
The cognitive bias begins when Tony credits Dr. Bob Hariri with discovering stem cells in placentas doomed for the dumpster. Then Bob tosses “autologous fat-stem cells” into the medical waste in two ways. He fails to mention:

1. Zuk et al.’s 1999 discovery in a UCLA lab that adipose tissue is the most accessible, abundant, and potent source of mesenchymal stem cells (MSCs), and

2. Adipose tissue contains a mixed population of stem cells and other regenerative cells. Researchers call these autologous Adipose-Derived Regenerative Cells or ADRCs.

He reasons that stem cells from bone marrow, skin, or adipose tissue decline in number and potency as we age. Hariri calls this process stem cell exhaustion. Thus, he argues cultured allogeneic or donor placental-derived MSCs (PD-MSCs) are pristine. Umbilical-cord-derived MSCs (UC-MSCs) are next best. The hypothesis is making sense – so far.

But just because it’s logical doesn’t mean it’s true. James Willerson, MD, Ph.D., and Emerson Perin, MD, Ph.D., from Texas Heart Institute, contradicted Bob’s argument in Buying New Soul (2012).[1]

“Adipose tissue seems to be a promising source of stem cells…The resiliency of adipose tissue is evidenced by patients’ ability to gain weight easily even in the presence of multiple comorbidities known to inhibit stem cell function. It may be that certain tissues are less exposed to the detrimental effects of disease and aging.”

Notably, investigators have published over 85,000 papers discussing adipose-derived stem cells (ADSCs). That is an average of 11 new publications per day over the past 22 years. The publishing rate has accelerated to 36 per day, nearly four times the historical average.

A PubMed search finds less than half as many publications on Placenta-derived stem cells (PDSCs).

Jack Nicklaus’ Stem Cell Therapy Hole-in-One
After Bob gave fat a lousy score, Tony recounted meeting Jack Nicklaus at the Vatican Stem Cell Summit. Here, Jack told the audience about his stem cell therapy hole-in-one. Stem cells “helped me go from not being able to stand for longer than 10 minutes, to playing golf and hitting the tennis ball again without pain. They will dramatically enhance your life!”

Apparently, Tony didn’t know prof Dr. Eckhard Alt treated Jack’s back with ADRCs. The your-fat-stem cells-are-too-old theory missed the cut here: Jack was in his late 70s when he opted to go to Germany for autologous ADRCs.

Note, Jack said “helped me” – stem cells are the fertilizer – physical therapy, appropriate exercise, and a healthy lifestyle are the gardeners that restore health.
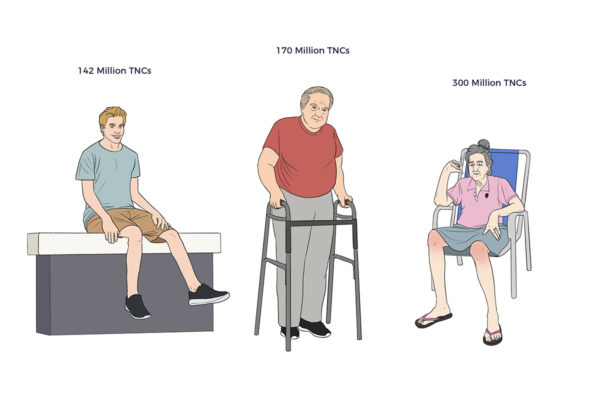
Finally, our groups in the Bahamas and the U.S. have treated ~400 patients with ADRCs.

We counted every patient’s total nucleated cell (TNCs) with the NucleoCounter. A TNC contains DNA, which makes the cell active. Red blood cells do not have a nucleus and thus have no therapeutic effect. A review of the stats proves Dr. Willerson’s point: ADRCs’ yield, viability, and, most important, outcomes do not suffer from age.

Two over-70 patients with multiple morbidities hold the male and female records for highest yields and viability.

  • Nancy, a skinny long-term smoker with COPD, arthritis, and dermatitis, and
  • Bob, an obese man with polyarthritis, a rare neurologic condition, migraine headaches, and frailty.

On the other side of the coin, a 15-year-old spinal cord injury patient’s yield was right up there with Bob. Six months post-cell therapy and more than one year after his catastrophic injury, the young man regained bilateral motor control of his hip flexors and quads. Standard of Care SCI patients plateau at about 12-months – remarkably, this young man’s path is accelerating.

Most profound, our patients with multiple chronic conditions, including diabetes, heart, kidney, and autoimmune diseases – including obese patients – report high patient satisfaction.

Back to Tony’s story
Three specialists advised surgery. Then one injected PRP but must have hit a nerve as Tony’s arm went limp while performing. Next, a doctor recommended Pulsed Electro-Magnetic Field Therapy (PEMF). PEMF helped: His pain score reduced to 4.5. Tony continued PEMF until he arrived in Panama. Presumably, his pretreatment score pain was lower still.

The Panama clinic gave him three IV shots of umbilical cord-derived mesenchymal stem cells (UB-MSCs) over three days. On the first day, a doctor injected stem cells into his shoulder – but not his back.

On day two, Tony had an adverse event: “…I had what’s often called a “cytokine response.” I felt chills and shaking, but I wasn’t scared. They told me it was normal: “Your body’s healing, just get some rest.”

At the risk of offending Tony or the clinic staff: A cytokine response is an abnormal reaction.    The body’s immune system recognized the donor stem cells as foreign (or contaminated). These reactions do not occur with autologous ADRCs.

By the way, we respect Neil Riordan, Ph.D., CEO of the Stem Cell Clinic of Panama. He co-authored three early, highly cited papers on stromal vascular fraction (the generic term for ADRCs).

Recent research clarifies that donor stem cells are “immune-evasive, not immune-privileged,” counter to the proponents of allogeneic cell therapy.[2] [3] Simply put, the Panamanian UB-MSCs and Tony’s immune system were not a perfect match. Married couples fight from time to time but can still be happy. Perhaps, that was the case with Panama clinic’s Golden Cells. They had a little spat and got on with it.

Thankfully, Tony says the shaking lasted 20 minutes. He did not allow how long the chills lasted or if he caught a fever. Published clinical trials report allogeneic MSC infusions often cause transient fevers. This side-effect is mild, particularly compared to the risks of surgeries, drugs, and devices.

Miraculously, 15 years of back pain and shoulder pain were gone for good on the third day, Tony stated. He does not specify if the injection doctor was board-certified in pain management. Of if the shoulder injections were done under ultrasound? As one reads on, the story gets confusing.

The stem cells took effect on day three – but we don’t know for how long or how much.

And here is the rub: The continuing story makes it hard to attribute the awe-inspiring, new-life proclamation to life force UB-MSCs alone. That is ok – if Tony’s fans understand that. First, his shoulder may not have been in that much pain, thanks to the PEMF and conventional care, i.e., ice, PT, and rest. And resting during the three-day protocol may have decompressed his spine.

Plus, he indulges in multiple biohacks per day for pain and inflammation.

Here is the point: Unrealistic expectations lead to disappointed patients. But they are thrilled when stem cell therapy helps them live a better life.

As Tony’s research, therapy, and investment journey twists and turns like Jack’s back did when he played the PGA tour, Tony accesses innumerable tools for his health:

  • Cryo-therapy,
  • Counter-strain physical therapy,
  • Laser therapy
  • Hyperbaric oxygen therapy,
  • PEMF therapy
  • Egoscue exercises,
  • Supplements,
  • Sauna,
  • Exosomes,
  • Stem cells, etc.

Last but not least, his story double-bogeyed with exosomes, nano-sized sacs of growth factors secreted from MSCs. “I personally used exosomes along with stem cells to address a variety of challenges I experienced as a result of the work I had done on my shoulder that I told you about in Chapter 2,”

What? Tony said Panama stem cells resolved those challenges on Day Three.

For reasons best known to biohackers and God, there is a growing misbelief that exosomes are more effective than MSCs. That science discussion is beyond the scope of this review. Suffice to say, MSCs release exosomes, growth factors, hormones, and anti-inflammatory cytokines in a single dose.

Significantly, ADRCs secrete hundreds more healing or trophic factors than cultured MSCs do alone.[4]  All these attributes place clinical-grade ADRCs at the top of the leader board.

However, that doesn’t mean PD-MSCs, UB-MSCs, and BM-MSCs aren’t effective. They can shoot par. But safety and effectiveness depend on complying with Good Lab Practices (GLPs), the culturing method, and other technical specifications. Pew Trusts exposed contamination-related adverse events when doctors treat patients with cheap and cheerful stem cell products.

AMBROSE’s use of the Celution™ cell processing system and compliance with the Federal Right to Try Act of 2017 underpins our pristine cell-related safety record.

Tony is a Humanitarian. He has inspired millions of people to live better lives and means Life Force to do the same thing. His 1100-page 17-hour listen does so.

However, he diluted his sincere intentions with cognitive bias, contradictory evidence, conflicts of interest, and hyperbole. Our forensic review of the stem cell commentary suggests other information in the book suffered the same fate.

Life Force is a best-seller.

[1] J. Willerson and E. Perin Buying New Soul J Am Coll Cardiol. 2012;60(21):2250-2251

[2] Berglund et al. Immunoprivileged no more: measuring the immunogenicity of allogeneic adult mesenchymal stem cells Stem Cell Research & Therapy (2017) 8:288

[3] Akrum et al Mesenchymal stem cells: immune evasive, not immune privileged Nat Biotechnol. 2014 March ;32(3):252–260

[4] Hirosi Y et al. Comparison of trophic factors secreted from human adipose-derived stromal vascular fraction with those from adipose-derived stromal/ stem cells in the same individuals

AMBROSE Cell Therapy

Your Right to Try

Retinitis Pigmentosa Hypothesis

Retinitis Pigmentosa Hypothesis

Retinitis Pigmentosa Hypothesis

Summary
Here, we hypothesize that autologous Adipose-Derived Regenerative Cells (ADRCs) is a new option for patients living with retinitis pigmentosa. In contrast to a drug with a single mechanism of action, ADRCs regulate the multiple factors contributing to a patient’s loss of eyesight.

Background16
In 1857, Dr. Donders identified a group of incurable eye disorders he named retinitis pigmentosa (RP). But it was not as simple as that: Subsequently, researchers discovered over 100 genes that can contain mutations leading to retinitis pigmentosa. But genetic abnormalities do not clarify everything; half of RP cases lack previous family history and explanation.
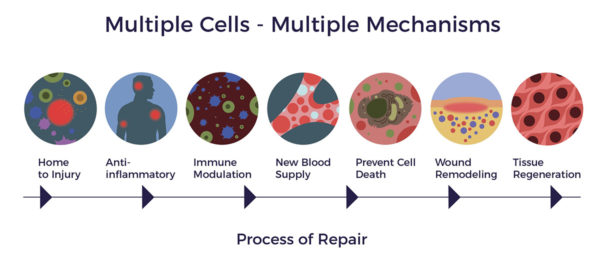
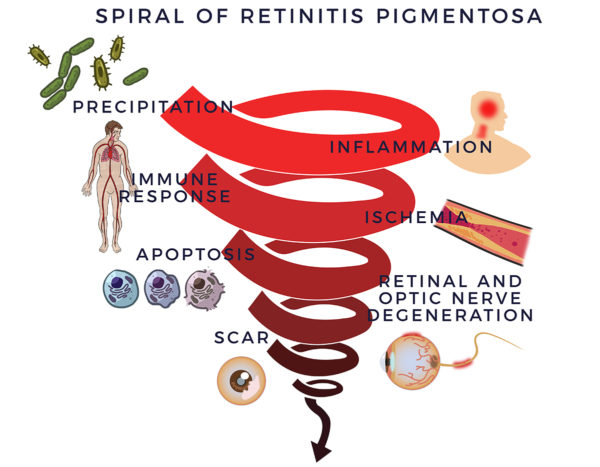
Yet, despite the disease’s complexity, able investigators have mapped out RP’s degenerative process. Retinitis means inflammation of the retina. That inflammation leads to a spiral of degeneration of the retina and optic nerve.

ADRC Repair Process
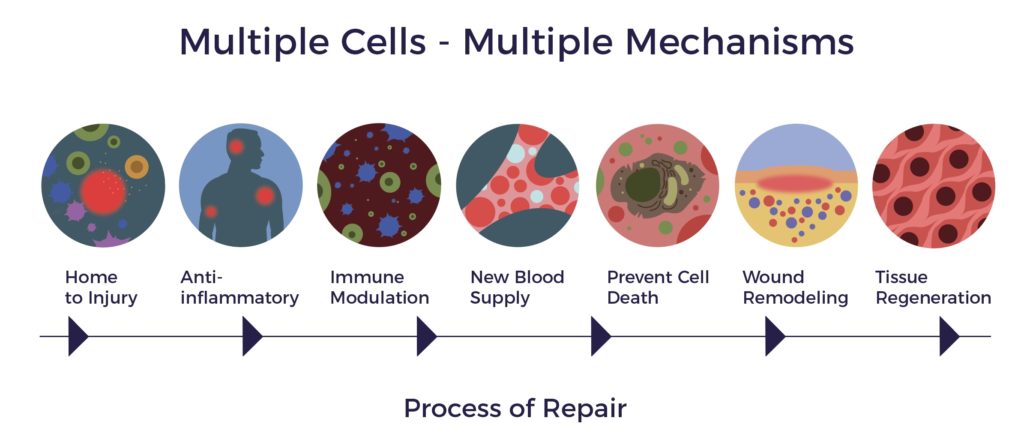
In the presence of infection, injury, or disease, ADRCs home to sites of inflammation and initiate a repair process through multiple mechanisms of action.

Time For a New Option
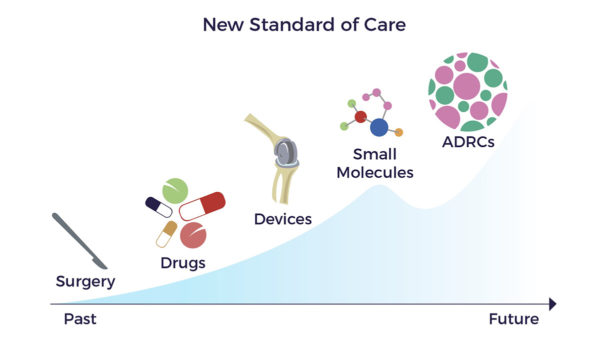
Drug and gene therapy developers continue to pursue the failed “one molecule or gene for one disease model” for RP. This minimalist approach has not produced a drug or gene therapy that changes disease progression or improves patients’ best-corrected visual acuity (BCVA).
In the real world, the 100,000 people in the US diagnosed with RP lack an option that slows, stabilizes, or reverses the disease’s progression. Instead, most are legally blind by age 40. Therefore, patients need a new standard of care regardless of the gene mutation or other culprit causing RP.

Hypothesis
Here, we hypothesize that autologous Adipose-Derived Regenerative Cells (ADRCs) is a new option for patients living with retinitis pigmentosa. In contrast to a drug with a single mechanism of action, ADRCs regulate the multiple factors contributing to a patient’s loss of eyesight.

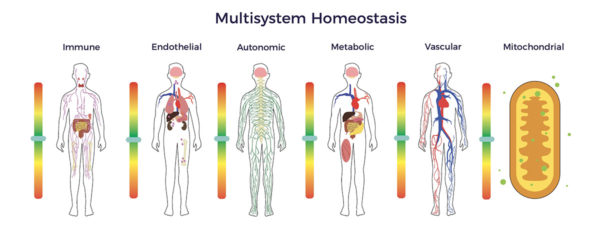
The cornerstone of our hypothesis is that all the body’s systems are interrelated and dependent. As such, multisystem dysfunction contributes to degenerative diseases, including RP [1] [2] [3] [4] [5]

Specifically, RP-related multisystem dysregulation results in:

  1. Oxidative stress,
  2. Reduced nitric oxide levels,
  3. Elevated systemic inflammation,
  4. Abnormal immune response,
  5. Metabolic dysregulation,
  6. Endothelial dysfunction and
  7. Mitochondrial impairment, and
  8. Autonomic dysfunction.[6] [7] [8] [9]

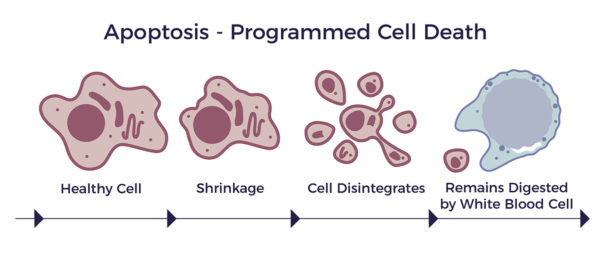
These abnormalities lead to apoptosis of the retinal photoreceptors and blindness. [10]

IV Protocol Rationale
We propose IV delivery of ADRCs based on:

  1. A rat study mimicking human RP demonstrated that IV infusion is superior to subretinal delivery. “It would appear that stem cells exert their effect over the whole retina when administered systemically. In comparison, subretinal delivery of cells including bone marrow-derived cells usually results in rod and cone rescue” (S. Wang 2010) [11]
  2. A human study of Umbilical Cord MSCs (UCMSCs) confirmed systemically-delivered stem cells’ feasibility, safety, and benefit. “Most patients improved their best-corrected visual acuity (BCVA) in the first three months. The proportions of patients with improved or maintained BCVA were 96.9%, 95.3%, 93.8%, 95.4%, 90.6%, and 90.6% at the 1st, 2nd, 3rd, 6th, 9th, and 12th-month follow-up, respectively. Most of the patients (81.3%) maintained or improved their visual acuities for 12 months.” (T. Zhao 2020). The researchers also proposed that the breakdown of the blood-retinal-barrier (BRB) in the progression of RP makes it possible that infused cells can reach the impaired retinal tissue without the need for injections directly in the eye. [12] [13] [14]
  3. A study of IV injection of USMSCs vs. direct injection of a steroid showed, “UCMSC intravenous infusion shows slow but persistent action in alleviating ME (macular edema) and can improve the visual function for a longer time.”.[15]
  4. A Japanese group compared the trophic factors secreted from fresh ADRCs vs. cultured ASCs (adipose-derived MSCs) from the same person. The study indicates that ADRCs are more multifunctional and potent than cultured ASCs cells. ADRCs released a greater variety of cytokines or soluble proteins at significantly higher amounts than ASCs. [16]
    The favorable comparison noted above extends to MSCs derived from other sources such as bone marrow, umbilical cord, and placenta.
  5. Conversely, several direct injection studies reported adverse events such as retinal tears and fibrosis. Therefore, both the safety profile and IV infusion pathways show advantages.

AMBROSE Protocol for Retinal Diseases:

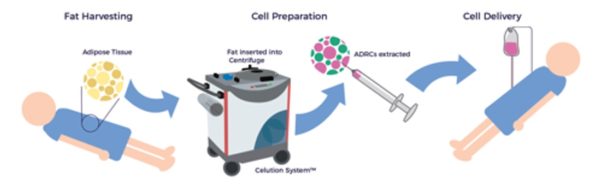
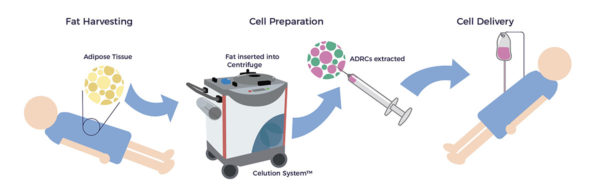
  1. A board-certified plastic surgeon, using water-assisted liposuction (WAL), harvests 400 ccs of lipoaspirate. WAL is minimally traumatic on the patient and tissue, resulting in higher ADRC yields and viability.
  2. The Celution system liberates the ADRCs from the lipoaspirate.
  3. A nurse inserts an IV and delivers mannitol. Mannitol is a sugar alcohol that temporarily disrupts the BRB. It is a standard of care for delivering drugs into the back of the eye.
  4. The ADRCs are delivered intravenously over a 20-minute infusion.

The outpatient procedure takes about five hours. Of that time, cell preparation takes 2.5 hours, during which the patient rests comfortably.

ADRCs
Adipose-Derived Regenerative Cells (ADRCs) is the designation for a clinical-grade preparation of stromal vascular fraction (SVF). ADRCs’ inherent role is maintaining cellular, tissue, and systemic homeostasis.[17] [18] [19]

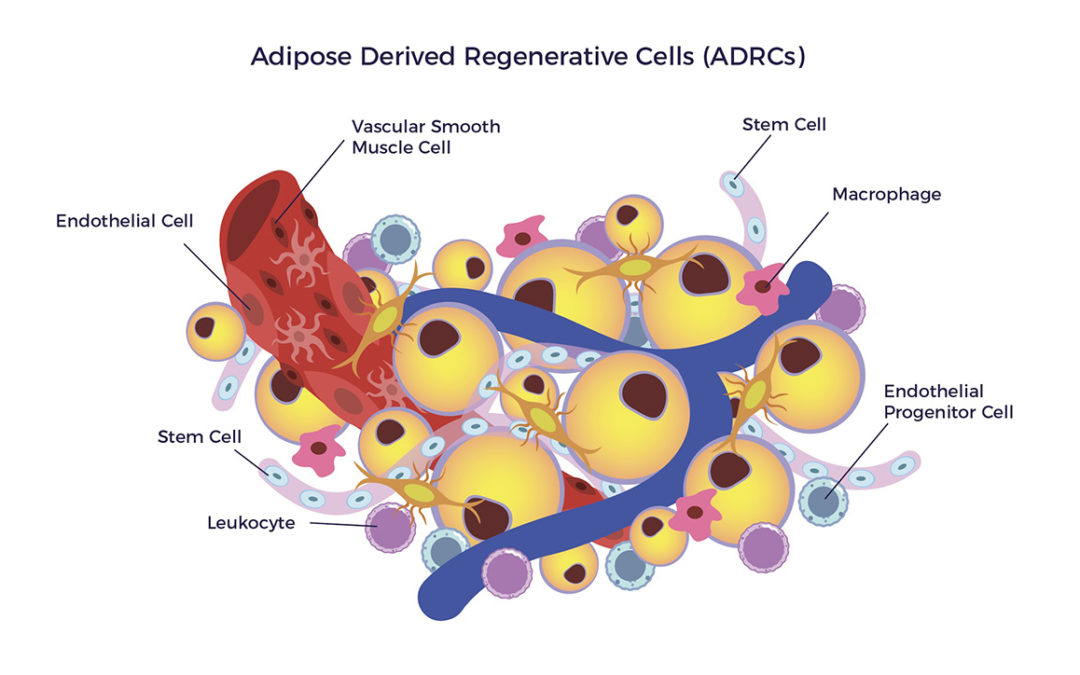
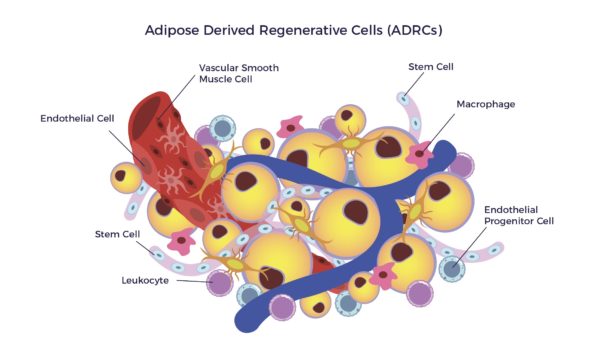
ADRCs are a heterogeneous population of cells, including mesenchymal stem cells, other progenitor cells, fibroblasts, T-regulatory cells, and macrophages. The mix includes a high percentage of endothelial cells, endothelial progenitor cells, macrophages, and leukocytes.
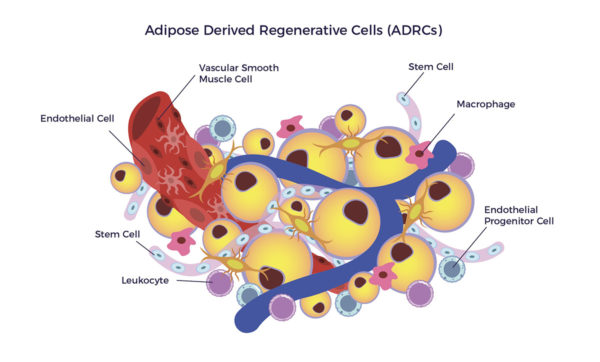
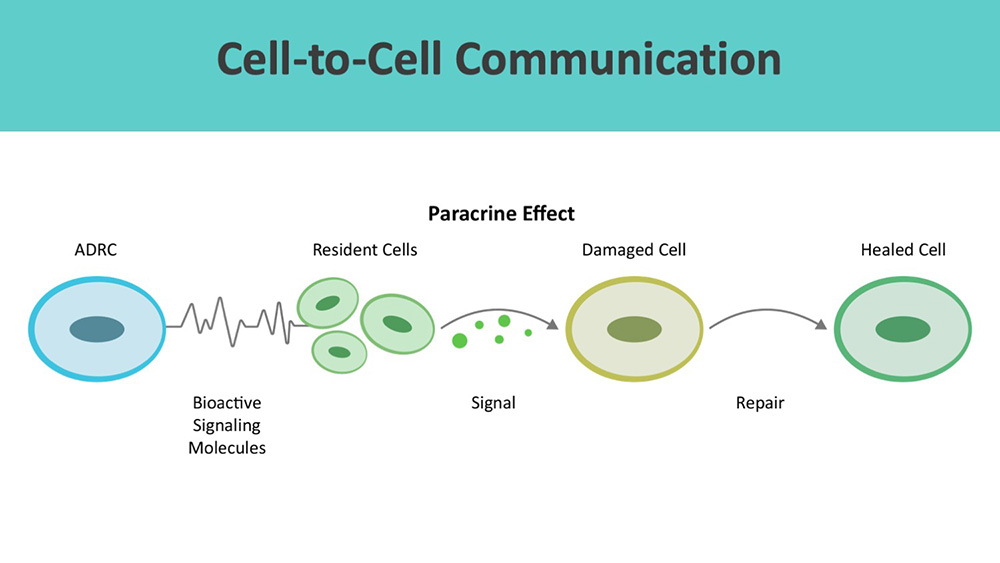
After homing to an inflammatory signal, the ADRC-secretome releases hundreds of cytokines and growth factors to the diseased microenvironment. The endogenous cells send signals back to the ADRCs.
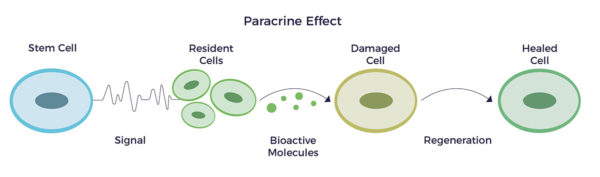
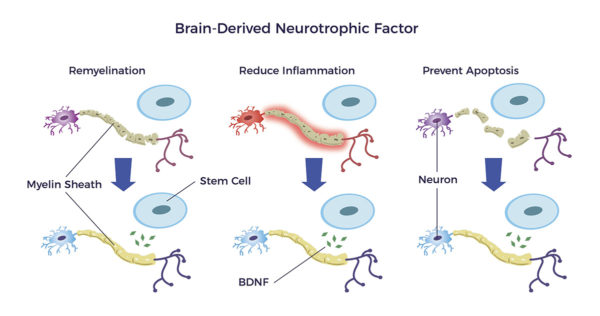
This crosstalk instructs the individual cell types necessary for repair to activate – and those not needed (or harmful) to stand down. Put differently, the plethora of biological agents in the secretome restores cellular stability and homeostasis.

ADRCs – Miracle-Gro for Nerve Repair
Miracle-Gro feeds your garden’s soil with the nutrients it needs to grow healthy roots, stems, petals, and leaves. Just as there are situations in which we fertilize a plant lacking vital nutrients, ADRCs secrete growth factors essential to the health of our aging brains, hearts, muscles, nerves, and so on. [20]

One such growth factor group is “Neurotrophic factors (NTFs).” Neuro relating to nerve and trophic, from Ancient Greek trophikós, meaning “of food or nourishment.” In other words, NTFs feed our neurons and nerves with nutrients.

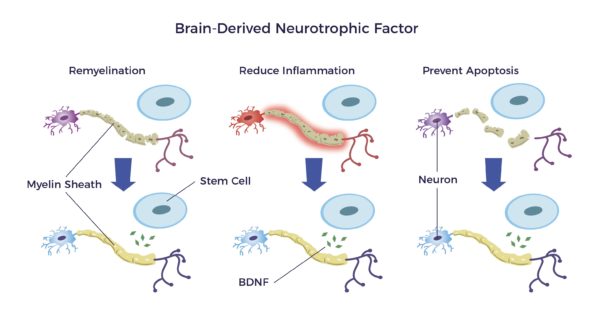
Notably, Brain-Derived Neurotrophic Growth Factor (BDNF) stimulates new neurons, nerve cell connections, and nerves. It also repairs the myelin sheathing surrounding the nerves. Further, this remarkable molecule is anti-inflammatory and anti-apoptotic. Diminished BDNF levels correlate with the progression of RP. [21] [22] [23] [24] [25]

A recent discovery of neuroimmune cells in ADRCs is notable. Neuroimmune cells innervate tissues and release BDNF.[26] Additionally, other cytokines in adipose tissue secrete an abundance of neurogenerative factors.

 Human studies show ADRCs release factors that:

  • Down-regulate inflammatory-autoimmune markers, including but not limited to TNF-A and TH17,
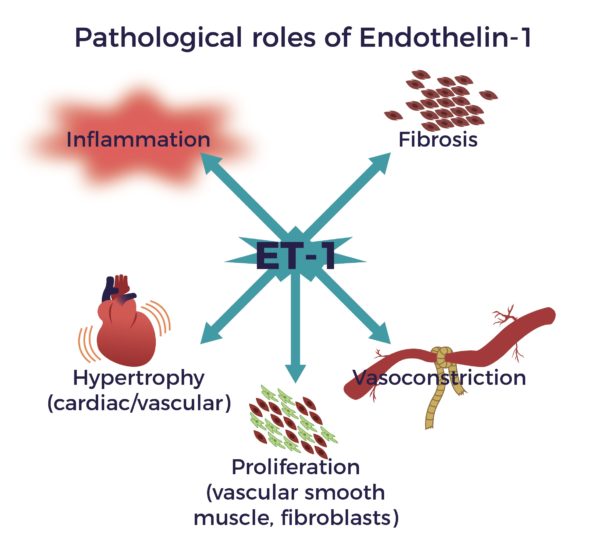
  • Reduce the production of Endothelin-1, a known constrictor of blood vessels and a culprit in subsets of RP patients.
  • Include Placental Growth Factor (PGF), Stromal-Derived Factor-1 (SDF-1), and Vascular Endothelial Growth Factor (VEGF), all of which assist in the growth and stabilization of new blood vessels. These GFs are also anti-inflammatory and anti-apoptotic.
  • Promote the switch from inflammatory macrophages (M1s) to anti-inflammatory macrophages (M2s) such as prostaglandin E2 (PGE2).

Permeating the Blood-Retinal-Barrier
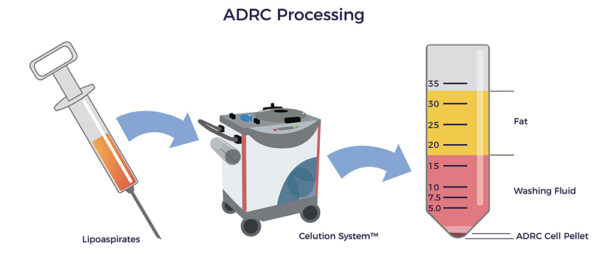
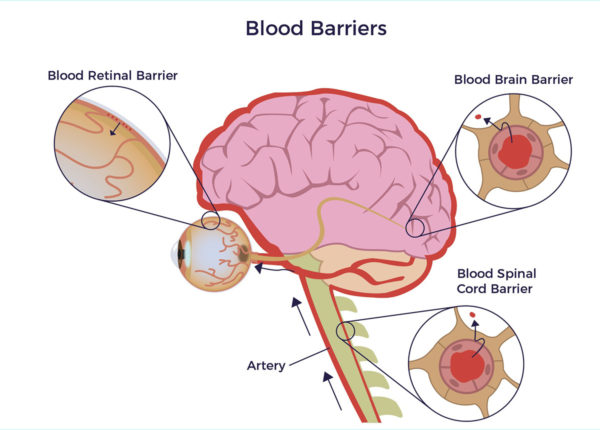
A critical concern of physicians and patients regarding ocular diseases is whether adult stem cells can be delivered non-invasively and safely permeate the blood-retinal-barrier (B-R-B), an extension of the blood-brain-barrier. The B-B-B protects our brains, eyes, and the spinal canal from microbial invaders. It is our central nervous system’s version of Fort Knox. Still, instead of a granite-lined concrete structure, epithelial and endothelial cells line the outer and inner blood-retinal-barrier, respectively. [27]

Three mechanisms allow the migration of MSCs and the ADRC secretome into the back of the eye.

  1. Mannitol, a safe sugar alcohol, temporarily opens the B-B-B.
  2. ADRCs release cytokines that permeate the B-B-B,
  3. MSCs possess the ability to cross the B-B-B. [28] [29]

As the lymphatic vessels parallel the vascular system, they may be a route that stem cells migrate from the spleen to bypass the blood-brain-barrier too. [30]

Age and ADRCs
Though aging is a failure of stem cells, ADRCs in the subcutaneous fat remain accessible, abundant, and potent throughout one’s life. (J. Willerson et al. Buying New Soul 2013) [31] Thus, autologous ADRCs are effective in elderly patients.

Safety
The Celution System® is a closed, sterile lab-in-a-box. Celution liberates autologous clinical-grade ADRCs from lipoaspirate at the point of care.

More than 40 countries have approved Celution for clinical use, including the United Kingdom, the European Union, Japan, South Korea, and New Zealand. Additionally, FDA has approved Celution for nine clinical trials.


Since 2007 approvals for Celution in Europe and Japan, no reported cell-related adverse events have been reported in reported trials, studies, and clinical use. [32]

[1] Dantzer R. Neuroimmune Interactions: From the Brain to the Immune System and Vice Versa. Physiol Rev. 2018;98(1):477-504.

[2] Tracey K The inflammatory reflex Nature Vol 420 19/26 December 2002

[3] Blaszkiewicz et al. The involvement of neuroimmune cells in adipose innervation Mol Med (2020) 26:126

[4] Simora N et al. The Role of the Immune System in Metabolic Health and Disease Cell Metabolism 25, March 7, 2017

[5] Amiya E MD PHD et al The Relationship between Vascular Function and the Autonomic Nervous System Ann Vasc Dis Vol. 7, No. 2; 2014; pp 109–119 Online Month May 16, 2014

[6] Okita A, Murakami Y, Shimokawa S, et al. Changes of serum inflammatory molecules and their relationships with visual function in retinitis pigmentosa. Invest Ophthalmol Vis Sci. 2020;61(11):30.

[7] Vinik A I The conductor of the autonomic orchestra June2012 Volume3 Article71 13

[8] Limoli P G et al. Antioxidant and Biological Properties of Mesenchymal Cells Used for Therapy in Retinitis Pigmentosa Antioxidants 2020, 9, 983

[9] Sorrentino FS, Bonifazzi C, Paolo P The Role of the Endothelin System in the Vascular Dysregulation Involved in Retinitis Pigmentosa Journal of Ophthalmology Volume 2015, Article ID 405234

[10] Murakami, Y et al, (2018), C-Reactive protein and progression of vision loss in retinitis pigmentosa. Acta Ophthalmol, 96: e174-e179.

[11] Wang S, Lu B, Girman S, Duan J, McFarland T, et al. (2010) Non-Invasive Stem Cell Therapy in a Rat Model for Retinal Degeneration and Vascular Pathology. PLoS ONE 5(2): e9200.

[12] Zhao T et al. Intravenous Infusion of Umbilical Cord Mesenchymal StemCells Maintains and Partially Improves Visual Function in Patients with Advanced Retinitis Pigmentosa STEM CELLS AND DEVELOPMENT Volume 29, Number 16, 2020

[13] Grant ZL et al. Blocking endothelial apoptosis revascularizes the retina in a model of ischemic retinopathy J Clin Invest. 2020;130(8):4235-4251

[14] Lang M et al. Vascular dysfunction in retinitis pigmentosa Acta Ophthalmol. 2019: 97: 660–664

[15] Zhao T, Lie H, Wang F, Liu Y, Meng X, Yin Z and Li S (2021) Comparative Study of a Modified Sub-Tenon’s Capsule Injection of Triamcinolone Acetonide and the Intravenous Infusion of Umbilical Cord Mesenchymal Stem Cells in Retinitis Pigmentosa Combined With Macular Edema. Front. Pharmacol. 12:694225.

[16] Hirose Y et al. Comparison of trophic factors secreted from human adipose-derived stromal vascular fraction with those from adipose-derived stromal/stem cells in the same individuals Cytotherapy, 2018; 20: 589–591

[17] S Kesten and JK Fraser Autologous Adipose Derived Regenerative Cells: A Platform for Therapeutic Applications Advanced Wound Healing Surgical Technology International XXIX

[18] Visoso F. J. et al Mesenchymal Stem Cells in Homeostasis and Systemic Diseases: Hypothesis, Evidences, and Therapeutic Opportunities Int. J. Mol. Sci. 2019, 20, 3738

[19] Caplan A I Mesenchymal Stem Cells: Time to Change the Name! STEM CELLS TRANSLATIONALMEDICINE 2017; 6:1445–1451

[20] A Caplan PhD MSCs: The Sentinel and Safe-Guards of Injury J. Cell. Physiol. 231: 1413–1416, 2016.

[21] Razavi, Shahnaz et al. “Neurotrophic Factors and Their Effects in the Treatment of Multiple Sclerosis.” Advanced Biomedical Research 4 (2015): 53. PMC. Web. 28 Sept. 2018.

[22] J. K. Huang et al Myelin Regeneration in Multiple Sclerosis: Targeting. Endogenous Stem Cells., The American Society for Experimental NeuroTherapeutics, Inc. 2011

[23] T Lopatina et al. (2011) Adipose-Derived Stem Cells Stimulate Regeneration of Peripheral Nerves: BDNF Secreted by These Cells Promotes Nerve Healing and Axon Growth De Novo. PLoS ONE 6(3): e178991

[24] S.  Seigo et al, Uncultured adipose-derived regenerative cells promote peripheral nerve regeneration, Journal of Orthopaedic Science, Volume 18, Issue 1,2013, Pages 145-151

[25] Xu et al Brain-derived neurotrophic factor reduces inflammation and hippocampal apoptosis in experimental Streptococcus pneumoniae meningitis Journal of Neuroinflammation (2017) 14:156

[26] Blaszkiewicz, M., Wood, E., Koizar, S. et al. The involvement of neuroimmune cells in adipose innervation. Mol Med 26, 126 (2020)

[27] Campbell M, Humphries P. The blood-retina barrier: tight junctions and barrier modulation. Adv Exp Med Biol. 2012; 763:70-84.

[28] L. Liu et al From Blood to the Brain: Can Systemically Transplanted Mesenchymal Stem Cells Cross the Blood-Brain Barrier? Stem Cells International Volume 2013, Article ID 435093

[29] A. Laroni et al Mesenchymal stem cells for the treatment of neurological diseases: Immunoregulation beyond neuroprotection Immunology Letters 168 (2015) 183-190

[30] M. Absthina et al Human and nonhuman primate meninges harbor lymphatic vessels that can be visualized noninvasively by MRI eLife 2017;6: e 29738

[31] Perin EC and Willerson JT Buying New Soul J Am Coll Cardiol. 2012;60(21):2250-2251

AMBROSE Cell Therapy

Your Right to Try

The Power of Simplicity in Health and Wellness

The Power of Simplicity in Health and Wellness

The Power of Simplicity in Health and Wellness

We often undervalue the Power of Simplicity in our health and wellness.

At one end of the spectrum, the standard of care extends our lifespans, i.e., drugs, surgery, and devices.But the average senior sees seven doctors and takes seven meds per year. Thus, we all know someone – or are that someone – who lives with a poor quality of life.Self-proclaimed biohacking broscientists are on the other end of the spectrum.If something might just help your health – no proof required- one of the broscientists will sell or promote it. In doing so, they claim their products, equipment, books, podcasts, and psychedelic drugs are the solution to everything from chronic disease to healthy aging.


The Power of Simplicity
Instead, you can be the hero of your health by taking control of your mind and body with simple lifestyle practices. Better yet, these tools cost nothing but a bit of time. And they bring enjoyment to you and others with whom you live, work, and play.

The pillars of healthy aging are moderate exercise, an anti-inflammatory diet, a strong family, and fun, supportive friends. It’s “too simple.”

  • Study after study demonstrates walking would be a trillion-dollar drug – if big pharma could put it in a vial and sell it. Healthline says their top 10 benefits include heart health, lower blood sugar, boosted energy, living longer, creative thinking, and more.
    A trial led by the University of Massachusetts found that walking about three miles per day cut the risk of dying by more than half. Surprisingly, people who walked further or faster did not live longer. According to the Cleveland Clinic, too much exercise can hurt you. In other words, you don’t have to be a weekend warrior to be healthy.
  • The Harvard School of Public Health supports the age-old Mediterranean diet. If you start the Mediterranean diet before the age of 80, you will outlive at least three of your friends who eat the western diet. Our Italian, Spanish, and Greek friends who consume more olive oil, fruits, vegetables, nuts, and seafood than Americans have a lower risk of heart disease, stroke, dementia, and depression.
  • Dan Buettner studied five communities in Japan, Italy, Greece, Costa Rica, and California. In these five Blue Zones, more 90-year old’s live with vim and vigor than anywhere else on the planet. His talk, How to live to be 100+, ties together the common denominators regarding exercise, diet, community, and purpose that Buettner’s research unearthed. Suffice to say, people in these communities walk a lot.
  • At 33, Lissa Rankin, M.D., was a burned-out ob-gyn physician. She was taking seven medications to treat a whole host of conditions.  Her successful search for better personal health led Lissa to mind-over-body medicine.  In her TEDx Talk, Is there scientific proof we can heal ourselves?, Lissa names research studies that show friendships, long-term relationships, a positive frame of mind, and relaxation exceed the benefits of exercise and diet alone.
  • In Shut your Mouth and Change your Life, Patrick McKeown explains how simply switching from mouth breathing to nasal breathing improved his asthma, sleep, and focus. Gentle, slow nasal breathing enhances heart health, lung function, sexual fitness, immune strength, and a heightened sense of well-being. He gives new meaning to a breath of fresh air. And breathwork isn’t new: Medical research attributes the benefits of meditation and yoga to it.

But for some people, healthy living isn’t enough, or it came too late.  After failing conventional and integrative medicine, Barbara, Jeff, Tony, Trish, and others credit accessing their adipose-derived stem and regenerative cells (ADRCs) with their improved quality of life. In this way, ADRCs bring a Golden Era of Self-Cell Repair to healthcare.

In summary, these mind-body wellness tools are the keys to the healthspan kingdom.

Conversely, extreme biohacking may just be the new stupid.  In this realm, “broscience” geniuses Dave Asprey, Joe Rogan, and Ben Greenfield score healthcare IQs below the room temperature.

Like big pharma, biohacking is big business. If we stacked on top of one another all the equipment, products, supplements, coffee, food, books, course materials, franchise documents, blog posts, and transcripts the big three market, it would be the height of a 10-story super-store.

The polar opposites are the stars of the back-to-basics formula.  They are everyday folks who enjoy life into their 80s, 90s, and 100s with intact memories, healthy hearts, and rich social lives.
 

The millions of scientific papers supporting the Power of Simplicity in health could encircle the earth.On a personal basis, the pillars of the Power of Simplicity encompass the future of healthy, happy, and dignified aging. And you can splurge on them without having to spend any money at the Biohacking Superstore.
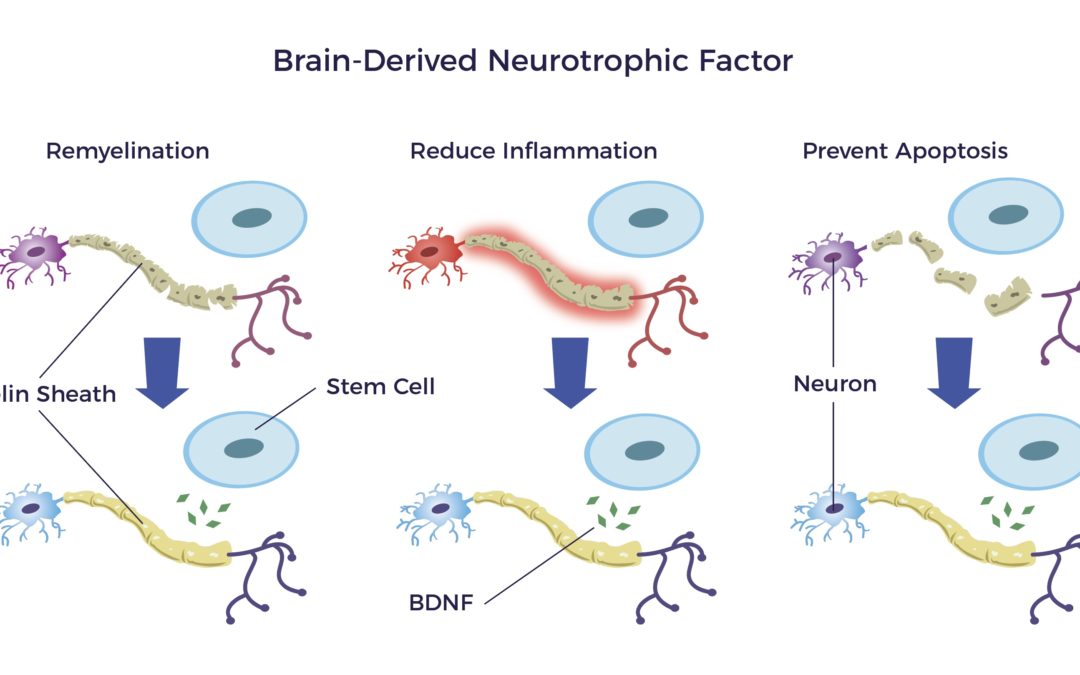
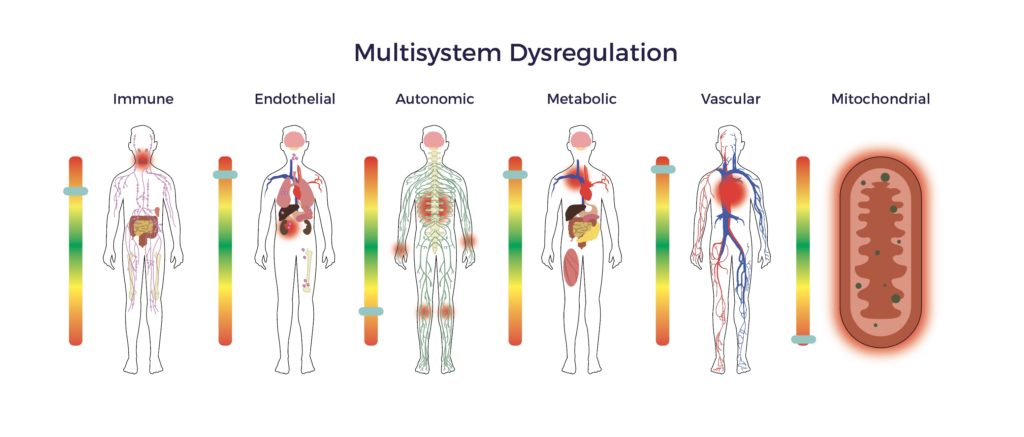
AMBROSE Cell Therapy

Your Right to Try

Spinal Cord Injury Cell Therapy Hypothesis

Spinal Cord Injury Cell Therapy Hypothesis

Spinal Cord Injury Cell Therapy Hypothesis

Background: In December 2018, AMBROSE Cell Therapy pioneered a novel protocol for Jeff, a patient living with a spinal cord injury. Jeff’s 14-month patient-reported outcome chronicled significant improvements in symptoms, function, and quality of life.

In December 2017, Jeff’s spine surgery gone wrong resulted in an SCI and paraplegia. His extended hospitalization led to an abscessed colon requiring an ileostomy.  Compounding matters, he lived with T2 diabetes.

Jeff complained of neck and back pain, neuropathy, scar pain from the ileostomy, claw toes, spasticity, poor balance, diabetes T2, shoulder immobility, and erectile dysfunction (ED).  He took seven meds to manage his symptoms, including opioids.

Our in-depth review of published SCI stem cell therapy studies yielded positive results. Thus, AMBROSE curated the literature and developed a personalized protocol for Jeff.

The treatment strategy was unconventional. Rather than only targeting the spinal cord lesion, the AMBROSE medical team addressed Jeff’s array of complaints in a single procedure using a Master Protocol.

In essence, AMBROSE designed one overarching protocol to treat multiple issues in a single treatment including the injury site, using adipose-derived regenerative cells (ADRCs). Our treatment team then personalizes it for each patient.

Importantly, our previous group’s prior successes using a Master Protocol with over 300 patients living with diverse chronic conditions supported our hypothesis.  (Okyanos Cell Therapy, Bahamas 2014- 2017).

In addition:

  • A subsequent meta-analysis, Transplantation of mesenchymal stem cells for spinal cord injury: a systematic review and network meta‑analysis, validated the safety and effectiveness of MSC-based treatments for SCI. [1]
  • Researchers had published successful case reports using injections of micronized adipose tissue to address SCI-related musculoskeletal conditions, scar pain, and neuropathy. [2] [3]
  • Published trials for other chronic conditions informed.[4] [5]
  • Urology KOLs advised on a sacral-plexus injection sub-protocol to target bladder and bowel dysfunction.

Hypothesis
A wide gap exists between the known pathophysiology of spinal cord injury and the standard of care being relied upon to treat it. Specifically, the damage to the cord incites multisystem dysregulation, including immune, endothelial, metabolic, mitochondrial, and autonomic dysfunction. [6] [7] [8]

Hence, patients suffer from an array of secondary complications.

Further, the overwhelming insult suppresses spinal cord regeneration, limiting functional recovery. Thus, the expected window of improvement for SCI patients is ~12 months.

As an example, Jeff’s symptoms included 24/7 scar pain, neuropathy, bilateral spasticity, bowel and bladder issues, ED, and impaired balance. At 11 months post-injury, Jeff and his physiatrist recognized his progress had leveled off.

Yet, drug discovery focuses on a single mechanism of action to repair the injury site or suppress a symptom. Put differently, the pharma model of one drug, gene, or cell type to treat a disease has made little progress in improving the prognosis for patients living with spinal cord injuries. This approach neglects a deep body of literature documenting the multiple factors and resulting comorbidities that combine to handicap patients like Jeff.

Multiple Mechanisms of ADRCs
In contrast, ADRCs have multiple mechanisms of action (MOAs) targeting all the factors involved in a chronic condition, including multisystem dysregulation. [9]

ADRCs home to sites of inflammation and secrete hundreds of bioactive molecules that are anti-inflammatory, immuno-modulatory, angiogenic, anti-apoptotic, and wound healing.

ADRCs work through cell-to-cell communication or the paracrine effect.

Beyond wound healing mechanisms, ADRCs restore cellular, systemic, and tissue equilibrium (multisystem homeostasis). [10] [11]

In Jeff’s recovery, the restoration of multisystem homeostasis included improved balance, pain scores, bladder, and bowel function, as well as a significant reduction in spasticity.  The net result was an elimination of all drugs, engaging in hardcore gym workouts, a return to racing, learning to fly helicopters and scuba diving, plus playing golf three times a week.  Though not cured or asymptomatic, Jeff is real-world evidence that ADRCs extended Jeff’s recovery window.

In sum, our preliminary evidence indicates that ADRCs can extend or restart the neurologic window of recovery by restoring multisystem homeostasis.

Why Adipose Tissue?
Unlike other tissue sources of adult stem cells, e.g., bone marrow, ADRCs remain accessible, abundant, and potent throughout one’s life. [12] Following liposuction, the Celution™ Cell Processing System (Lorem Cytori, Inc.) centrifuges the lipoaspirate and prepares the ADRCs.

 Why ADRCs

Adipose-Derived Regenerative Cells (ADRCs) are the designation for a clinical-grade preparation of stromal vascular fraction (SVF), a heterogeneous population of cells residing on the outer lining of the capillaries in adipose tissue. The cell mix includes MSCs, endothelial cells (ECs), endothelial progenitor cells (EPCs), fibroblasts, T-regulatory cells (Tregs), macrophages, and other immune cells (leukocytes).[13]

ADRCs secrete significantly higher amounts of trophic factors compared to Adipose-Derived MSCs (ADSCs).[14] Therefore, the ADRC secretome amplifies the MOAs of ADSCs, including but not limited to:

  • Anti-inflammation and Immuno-modulation,
  • Anti-apoptosis,
  • Angiogenesis,
  • Support of growth,
  • Differentiation of local stem cells and progenitor cells,
  • Anti-scarring, and
  • Chemoattraction.

Human studies show ADRCs:

  • Release factors that down-regulate inflammatory-autoimmune markers, including but not limited to TNF-A, TH17, IL6, and IL2, as well as upregulate IL10.
  • Promote the switch from inflammatory macrophages (M1s) to anti-inflammatory macrophages (M2s) via Prostaglandin E2 (PGE2) and the MSCs in the mix.
  • Reduce Endothelin-1 (ET-1), a known constrictor of blood vessels, implicated in spinal cord-blood-barrier disruption after the injury.

  • Assist in the growth and stabilization of new blood vessels by secreting placental Growth Factor (PGF), Stromal-Derived Factor-1 (SDF-1), and Vascular Endothelial Growth Factor (VEGF).

Notably, a close relationship exists between revascularization and improved functional outcomes after SCI. First, a well-vascularized lesion provides a permissive microenvironment for local tissue survival and nerve regeneration. Improved capillary blood flow, angiogenesis, and B-SC-B integrity facilitate functional recovery.[15] [16]

Neurotrophic factors
ADRCs deliver neurotrophic factors (NTFs) to the CNS, PNS, and ANS. Just as fertilizers keep plants healthy and growing, NTFs stimulate the development of new brain cells, brain cell connections, and nerves.
One such trophic factor is the brain-derived neurotrophic factor or BDNF.

BDNF:

  • Repairs the myelin sheathing surrounding the nerves
  • Reduces inflammation and,
  • Prevents apoptosis that results from an injury or disease. [17] [18] [19] [20] [21]

A recent discovery of neuro-immune cells in ADRCs connects their role in enhancing neuroplasticity.[22] [23]

Safety
Since 2007, no ADRC-related adverse events have been reported.[24]


[1] Chen et al Transplantation of mesenchymal stem cells for spinal cord injury: a systematic review and network meta‑analysis J Transl Med (2021) 19:178

[2] Cherian C et al. Autologous, micro-fragmented adipose tissue as a treatment for chronic shoulder pain in a wheelchair using individual with spinal cord injury: a case report Spinal Cord Series and Cases (2019) 5:46

[3] Huang S-H, Wu S-H, Lee S-S, Chang K-P, Chai C-Y, Yeh J-L, et al. (2015) Fat Grafting in Burn Scar Alleviates Neuropathic Pain via Anti- Inflammation Effect in Scar and Spinal Cord. PLoS ONE 10(9): e0137563

[4] A Nguyen, A et al Stromal vascular fraction: A regenerative reality? Part 1: Current concepts and review of the literature Journal of Plastic, Reconstructive & Aesthetic Surgery (2016) 69, 170e179

[5] Guo et al Stromal vascular fraction: A regenerative reality? Part 2: Current concepts and review of the literature Journal of Plastic, Reconstructive & Aesthetic Surgery (2016) 69, 180e188

[6] Sun et al. Multiple organ dysfunction and systemic inflammation after spinal cord injury: a complex relationship Journal of Neuroinflammation (2016) 13:260

[7] B. Perrouin-Verbe, C. Lefevre, P. Kieny, R. Gross, B. Reiss, M. Le Fort, Spinal cord injury: A multisystem physiological impairment/dysfunction, Revue Neurologique, Volume 177, Issue 5, 2021, Pages 594 605,

[8] Marion et al. Previously Identified Common Post-Injury Adverse Events in Traumatic Spinal Cord Injury—Validation of Existing Literature and Relation to Selected Potentially Modifiable Comorbidities: A Prospective Canadian Cohort Study JOURNAL OF NEUROTRAUMA 34:2883–2891 (October 15, 2017)

[9] Caplan A I Mesenchymal Stem Cells: Time to Change the Name! STEM CELLS TRANSLATIONALMEDICINE 2017; 6:1445–1451

[10] Visoso F. J. et al Mesenchymal Stem Cells in Homeostasis and Systemic Diseases: Hypothesis, Evidences, and Therapeutic Opportunities Int. J. Mol. Sci. 2019, 20, 3738

[11] Morris, M.E. et al. (2015), Systemically Delivered Adipose Stromal Vascular Fraction Cells Disseminate to Peripheral Artery Walls and Reduce Vasomotor Tone Through a CD11b+ Cell-Dependent Mechanism. STEM CELLS Translational Medicine, 4: 369-380.

[12] Perin EC and Willerson JT Buying New Soul J Am Coll Cardiol. 2012;60(21):2250-2251

[13]S Kesten and JK Fraser Autologous Adipose Derived Regenerative Cells: A Platform for Therapeutic Applications Advanced Wound Healing Surgical Technology International XXIX

[14] Hirosi Y et al. Comparison of trophic factors secreted from human adipose-derived stromal vascular fraction with those from adipose-derived stromal/ stem cells in the same individuals

[15]Yao C, Cao X and Yu B (2021) Revascularization After Traumatic Spinal Cord Injury. Front. Physiol. 12:631500.

[16] Numan MT et al. Autologous Adipose Stem Cell Therapy for Autonomic Nervous System Dysfunction in Two Young Patients. Stem Cells and Development 2017 26:6, 391-393

[17] Razavi, Shahnaz et al. “Neurotrophic Factors and Their Effects in the Treatment of Multiple Sclerosis.” Advanced Biomedical Research 4 (2015): 53. PMC. Web. 28 Sept. 2018.

[18] J. K. Huang et al Myelin Regeneration in Multiple Sclerosis: Targeting. Endogenous Stem Cells., The American Society for Experimental NeuroTherapeutics, Inc. 2011

[19] T Lopatina et al. (2011) Adipose-Derived Stem Cells Stimulate Regeneration of Peripheral Nerves: BDNF Secreted by These Cells Promotes Nerve Healing and Axon Growth De Novo. PLoS ONE 6(3): e178991

[20] S.  Seigo et al, Uncultured adipose-derived regenerative cells promote peripheral nerve regeneration, Journal of Orthopaedic Science, Volume 18, Issue 1,2013, Pages 145-151

[21] Xu et al Brain-derived neurotrophic factor reduces inflammation and hippocampal apoptosis in experimental Streptococcus pneumoniae meningitis Journal of Neuroinflammation (2017) 14:156

[22] O’Reilly ML and Tom VJ (2020) Neuroimmune System as a Driving Force for Plasticity Following CNS Injury. Front. Cell. Neurosci. 14:187.

[23] Blaszkiewicz, M., Wood, E., Koizar, S. et al. The involvement of neuroimmune cells in adipose innervation. Mol Med 26, 126 (2020)

[24] Lorem Cytori, Inc Unpublished internal data

AMBROSE Cell Therapy

Your Right to Try

A Golden Era of Cell-Assisted Diabetes Care

A Golden Era of Cell-Assisted Diabetes Care

A Golden Era of Cell-Assisted Diabetes Care

Amy’s Six-Year Patient-Reported Outcome Suggests So.

After living with severe diabetic neuropathy and fibromyalgia, in 2014, Amy, a then 24-year-old T1 diabetic, accessed the stem cells and other regenerative cells in her fat (adipose tissue) to improve her quality of life. That single treatment of adipose-derived regenerative cells (ADRCs) marked the turning point in Amy’s battle with diabetes. Amy’s every day went from being ruled by her foot pain to playing soccer, hiking the Grand Canyon, and living life to the fullest.

Amy didn’t go on a highly restrictive diet or make radical lifestyle changes on her way to improved symptoms, function, and quality of life. That isn’t to say those tools aren’t helpful for some; Amy just didn’t need them after cell therapy. Neither are we saying that her food choices and exercise regimens weren’t healthy; they just weren’t extreme.

To put Amy’s patient-reported outcome in perspective, let’s contrast it with the standard of care for chronic disease. A single dose of medicine rarely, if ever, provides lasting benefits. We often take prescribed drugs for life – unless they don’t work or the side-effects are not bearable by the patient.

Seniors, on average, take seven medicines and see seven doctors per year.

Those pursuing a more natural route take supplements daily, repeat integrative therapies for extended periods, go to the chiropractor when their bones and muscles go out of tune, and so forth.

The standard of care for people living with diabetes, concurrent with other diseases (co-morbidities) requires the patient to take multiple drugs daily to address each condition.

Not to be glossed over, Amy’s improvement for multiple morbidities resulted from a single, same-day treatment with ADRCs. Her benefits from cell therapy have now spanned more than six years and continue. If Amy needs a repeat treatment at some point or another, her win would still indicate a new standard of care for patients living with diabetes is afoot.

Or, as better put by Amy, instead of living in constant fear of her next flare, she can dream again. Broadly speaking, ADRC-based treatments bring creditable hope to people living with diabetes and related illnesses.

Notably, other tools can provide significant benefits to people with diabetes. For people living with T1D like Amy, continuous glucose monitoring (CGM) paired with an automated insulin pump makes a positive difference. For those with T2d, diet and managing blood sugars with CGM can change the disease’s progression or, if caught early enough, reverse it.

Amy’s self-cell therapy (using ADRCs) changed the course of her life. Her results and others like her signal that a Golden Era of  Diabetes Care has begun.

You can find Amy’s Patient-Reported outcome here.

AMBROSE Cell Therapy

Your Right to Try

If You Are Unique, Why are You Treated As an Average Patient

If You Are Unique, Why are You Treated As an Average Patient

If You Are Unique, Why are You Treated As an Average Patient

Kathy’s Patient-reported Outcome – Inherited Kidney Disease


“All happy families resemble one another, each unhappy family is unhappy in its own way.“
Leo Tolstoy

Like all patients with a chronic disease, Kathy was symptomatic in her own way. With 5% kidney function, regeneration was not an expectation. She faced a sure path to dialysis, to be followed by a kidney transplant. Kathy also had neck and hip pain. Just before starting dialysis, she exercised her Right to Try AMBROSE Cell Therapy.

Kathy’s patient-reported outcome provides a look at the unique benefits a patient can have by accessing one’s adipose (fat)-derived regenerative cells (ADRCs). Said differently, just as an individual’s symptoms differ, so are the improvements that can be achieved in one’s quality of life.

Our bodies are much the same as Tolstoy describes families. When we are healthy, we enjoy exercise, sleep well, and lead active lives. In health, we are all pretty much the same.

In contrast, a group of patients diagnosed with the same disease will have symptoms unique to each in their own way:

  • Many patients diagnosed with Parkinson’s disease have tremors, but others do not.
  • Heart disease may or may not include high blood pressure, irregular heart rhythms, hardening of the arteries, chest pain, or shortness of breath.
  • Some patients have arthritis in one joint, and others have multiple joints that are stiff and painful – not to mention possible bowel or skin issues.

When we ask “Dr. Google,” What causes fatigue and dizziness? a top search result lists nine possible causes.  Thus, diagnosis is problematic. Chronic conditions include different horns (symptoms) of the same devil (diagnosis). And different devils share many of the same horns.

As the Washington Post reported, Mayo Clinic found that more than 20 percent of patients are misdiagnosed by their primary care physician (PCP). But that is not because the PCPs do not meet Mayo’s standards. They get it wrong too.

The story goes on to explain, “Diagnosis is extremely hard,” said Mark L. Graber, a senior fellow at the research institute RTI International and founder of the Society to Improve Diagnosis in Medicine. “There are 10,000 diseases and only 200 to 300 symptoms.”

Mr. Graber’s stats help explain why there are so many disease spectrums. Our symptoms and how our bodies function (physiology) vary – even if we have the same diagnosis. Adding to the complexity, some patients have few if any symptoms, while others suffer badly with the same diagnostic findings. Most vexing, the degenerative process of one disease often leads to co-morbidities.

The Epic Failure of Large Clinical Trials – Solving for the Average
Despite the uniqueness of our physical complaints, the standard of care relies on clinical trials with thousands of patients. The goal is to determine an experimental drug, device, or surgery’s safety and efficacy. That makes sense – at least on the surface. The trouble is that large trials “solve for the average,” but you are not an average patient. There is no such thing. Our unique differences in mind, body, family history, and lifestyle determine which devils and which horns with which we might suffer.

Personalized medicine is trying to solve for the individual. Here doctors:

  • Use genetic testing to help determine the risk of inheriting a disease,
  • Assess your gut for bad actors underlying a chronic condition,
  • Evaluate inflammatory markers in your blood that may lead to heart disease, diabetes, or other illnesses, and so forth.

Though that approach is promising, little benefit for large populations has resulted from extensive testing. Why? Because doctors still rely on the standard of care, rather than personalized medicines, for prescribed treatments. Without personalized drugs, doctors have no choice but to solve for the average instead of the individual.

What does this mean in the real world?
In contrast to conventional medicines, ADRCs are unique to you. They are a personalized pharmacy residing in your body. Each cell in the ADRC population is in our blood, tissues, and organs, respectively. Their purpose in the body is to keep our bodily systems – vascular, immune, endocrine, and nervous systems – as well as our tissues in balance (homeostasis).

Admittedly, we can only make assumptions about why Kathy’s quality of life improved so much from AMBROSE Cell Therapy. Our thesis is that the IV of ADRCs brought her bodily systems toward homeostasis. The mechanisms may include, along with others, a systemic reduction in chronic inflammation and abnormal immune response aided by improved blood flow. Many other good things can result from such improvements. And the direct injections initiated a process of rescue and repair in Kathy’s neck and hip.[1][2]

At the end of the day, what matters most to Kathy is the improvement in her quality of life, despite the risk that it would worsen with dialysis and a kidney transplant.

[1] B.A. Tompkins et al Allogeneic Mesenchymal Stem Cells Ameliorate Aging Frailty: A Phase II Randomized, Double-Blind, Placebo-Controlled Clinical Trial J Gerontol A Biol Sci Med Sci, 2017, Vol. 72, No. 11, 1513–1521

[2]  S. Kesten & J.K. Fraser Autologous Adipose Derived Regenerative Cells: A Platform for Therapeutic Applications Advanced Wound Healing SURGICAL TECHNOLOGY INTERNATIONAL XXIX

AMBROSE Cell Therapy

Your Right to Try